Chapter25 Assessment of Cardiovascular Function
Overview of Anatomy and Physiology
Three layers
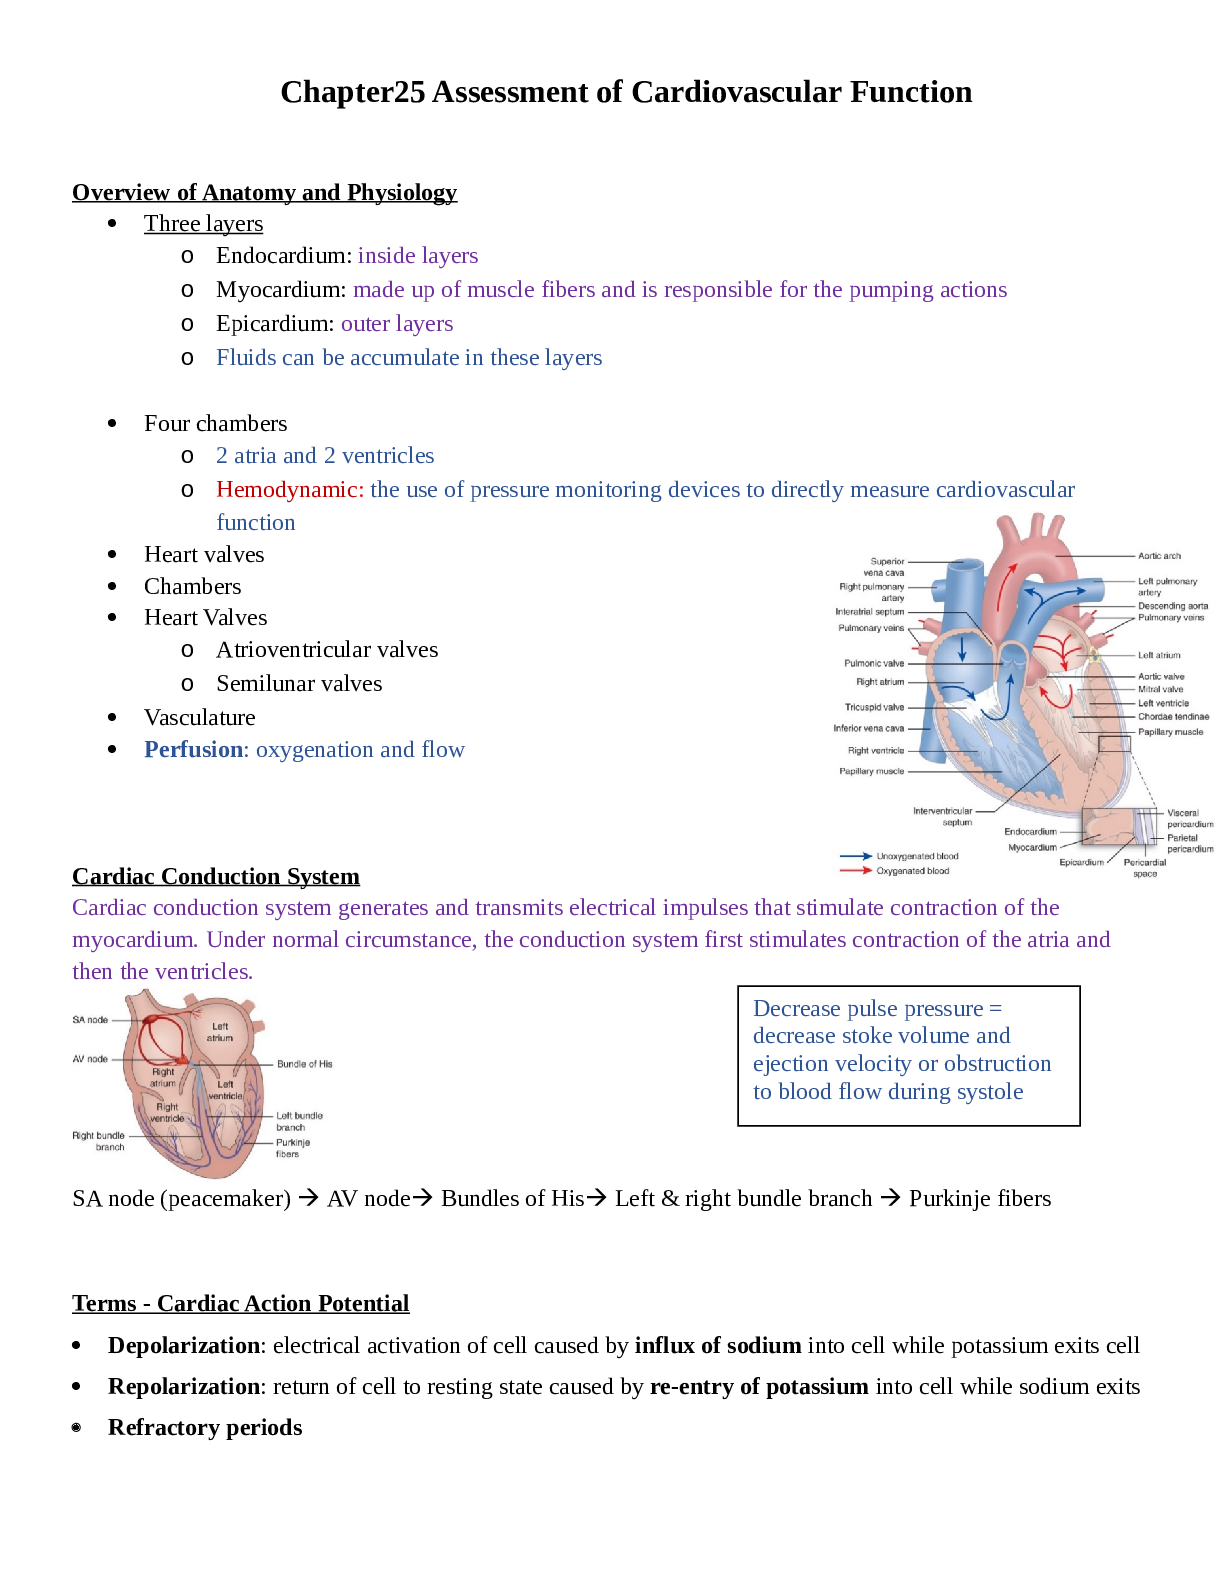
o Endocardium: inside layers
o Myocardium: made up of muscle fibers and is responsible for the pumping actions
o Epic
...
Chapter25 Assessment of Cardiovascular Function
Overview of Anatomy and Physiology
Three layers
o Endocardium: inside layers
o Myocardium: made up of muscle fibers and is responsible for the pumping actions
o Epicardium: outer layers
o Fluids can be accumulate in these layers
Four chambers
o 2 atria and 2 ventricles
o Hemodynamic: the use of pressure monitoring devices to directly measure cardiovascular
function
Heart valves
Chambers
Heart Valves
o Atrioventricular valves
o Semilunar valves
Vasculature
Perfusion: oxygenation and flow
Cardiac Conduction System
Cardiac conduction system generates and transmits electrical impulses that stimulate contraction of the
myocardium. Under normal circumstance, the conduction system first stimulates contraction of the atria and
then the ventricles.
SA node (peacemaker) AV node Bundles of His Left & right bundle branch Purkinje fibers
Terms - Cardiac Action Potential
Depolarization: electrical activation of cell caused by influx of sodium into cell while potassium exits cell
Repolarization: return of cell to resting state caused by re-entry of potassium into cell while sodium exits
Refractory periods
Decrease pulse pressure =
decrease stoke volume and
ejection velocity or obstruction
to blood flow during systole
o Myocardial cells must completely repolarize before they can depolarize again. During the
repolarization process. Two phases
o Effective refractory period: the cells is completely unresponsive to any electrical stimulus; phase in
which cells are incapable of depolarizing
Corresponds with the time in phase 0 to the middle of phase 3 of the action potential
o Relative refractory period: phase in which cells require stronger-than-normal stimulus to depolarize
Corresponds with the short time at the end of phase 3
Cardiac Action Potential
23.4: Cardiac action potential of a fasting-response Purkinje fiber. The arrows indicate the approximate time and
direction of movement of each ion influencing membrane potential. Ca++ movement out of the cell is not well
defined but is thought to occur during phase 4.
Great Vessel and Heart Chamber Pressures
25.2: great vessel and chamber pressures. Pressures are identified in
millimeters of mercury (mm Hg) as mean pressure or systolic or systolic over
diastolic pressure.
Cardiac Hemodynamics
CO= HR X SV
Hemodynamics
Terms - Cardiac Output
Stroke volume: amount of blood ejected with each heartbeat
o Average resting stoke volume is about 60 to 130 mL
Cardiac output: amount of blood pumped by ventricle in liters per minute
o In a resting adult is 4 to 6 L/min normally
Preload: degree of stretch of cardiac muscle fibers at end of diastole
o Preload is referred to as left ventricular
o End of diastole is the period when filling volume in the ventricles is the highest and the degree of
stretch of the muscle fibers is the greatest
o Less blood return to the heart reduced preload
o IV fluids will increase preload
Contractility: ability of cardiac muscle to shorten in response to electrical impulse
o Increased contractility result in increased stroke volume
o Contractility is depressed by acidosis, hypoxemia, and certain medication such as beta blockers
o Enhanced SNS, such as digoxin, epinephrine increase contractility
Afterload: resistance to ejection of blood from ventricle
o Arterial vasodilation decrease afterload increase stroke volume
o Arterial vasoconstriction increase afterload decrease stoke volume
Ejection fraction: percent of end diastolic volume ejected with each heartbeat
o Ejection fraction of normal left ventricle is 55% to 65%
HR
SV
Cardiac
Output
Stro
k
e
Volu
m
e
Preload
Afterload
Contractility
o Used as a measure of myocardial contractility
o Measured by echocardiogram
*Low heart rate will affect the cardiac output
*Stroke volume, if anything is affecting contractility the heart is not contracting, or heart is not
stretching/pumping will affect the cardiac output heart is not perfuse b/c CO is low
Age-Related Changes of the cardiac System
Atria
Left ventricles
o Myocardial thickening (hypertrophy) stiff and less compliant, and progressive decline cardiac
output = fatigue, decrease exercise tolerance, s4 may be present
o Left side heart failure- auscultating lungs sounds is cracks. Possible wheeze and gurgles
Valves
o Thickening or rigidly of the AV valves abnormal blood flow across the valves during cardiac
cycle = murmurs may be present
Conduction system
o Loss function slow heart rate
Sympathetic nervous system
Aorta and arteries
Baroreceptor response
Health History
Chief complaint
History of Present Illness
Past medical, surgical history
Past family history
Past social history
Home medications
Nutrition
Allergies
Physical Assessment
General appearance
o Evaluate the patient’s LOC & mental status
o Changes may be attributed to inadequate perfusion of the brain from a compromised cardiac
output of thromboembolic event (stroke)
o Observe for signs of distress (pain, discomfort, SOB, anxiety)
o Measure height and weight
Skin and extremities
o Skin color, temperature, and texture for problems with arterial or venous circulation
Blood pressure
Arterial pulses
Jugular venous pulsations (JVD)
o Right side heart failure fluid overload
o What does patient taking to improve fluid overload?
Heart inspection and auscultation
General assessment
Any deviations 偏差 from the normal?
o Do you have any change in activity tolerance?
o Heart as a pump
o Atrial/ventricular filling volumes
o Cardiac output
o Compensatory mechanisms
Did they change their shoes because their legs are swollen?
What position are they are laying to sleep?
Tripod position: patient falling a sleep on a chair - one sits or stands leaning forward and
supporting the upper body with hands on the knees or on another surface.
*right sided heart failure= Ascites, hepatojugular reflex, distention
Most Common Clinical Manifestations
Chest pain
Dyspnea
Peripheral edema, weight gain, abdominal distention
Palpitations
Fatigue
Dizziness, syncope, changes in level of consciousness
o Why would a patient be dizzy? Cardio output and perfusion issues
o LOC- due lack of oxygen to the brain
Chest Pain
Chest pain and chest discomfort are common symptoms that may be caused by a number of cardiac and
noncardiac problems summarizes the characteristics and patterns of common of chest pain or
discomfort.
Identify quantity of pain (0-10 SCALE)
Identify location of pain
Identify quality of pain
Radiation of pain
o Chest pain can radiate to left side, jaw, epigastrium, back, shoulder
Associated signs/symptoms (diaphoresis or nausea)
Duration of pain
o Severity or duration of chest pain does not predict the seriousness of its cause. For example,
when asked to rate pain using a 0 to 10 scale, patient with esophageal spasm may rate as 10. In
contrast, patient with MI, which is a potentially life-threatening event, may report 4 to 6.
Assess for other cardiac conditions
Assess for other significant conditions (see p. 663-664)
o Pneumonia, pulmonary embolism
o Hiatal hernia, GERD
Doctor will order labs or endoscopy on the patient to rules out GERD instead of heart
attack
o Costochondritis
o Vascular
Assessment
Medications
o Aspirin, a nonprescription medication is an important antithrombotic therapy for secondary
prevention in patients recovering from ACS (acute chest syndrome)
Nutrition
o Dietary modification, exercise, weight loss, and careful monitoring are important strategies for
managing three major cardiovascular risk factors: hyperlipidemia, hypertension, and diabetes.
o Diet restriction: sodium, fat, cholesterol, or calories.
o Height + weight
o BMI (assessment for obesity)
o Lab result: glucose, glycosylated Hb (diabetes), cholesterol, HDL, LDL, triglycerides
o Patient food habits and culture preference
Elimination
o Typical bowel and bladder habits need to be identified
o Nocturia (awakening at night to urinate) is common with HF patient
o Vagal maneuvers: try to slow down the fast heart rate by stimulate the vagal nerve
increase pressure to the baroreceptor to slow down HR
[Show More]