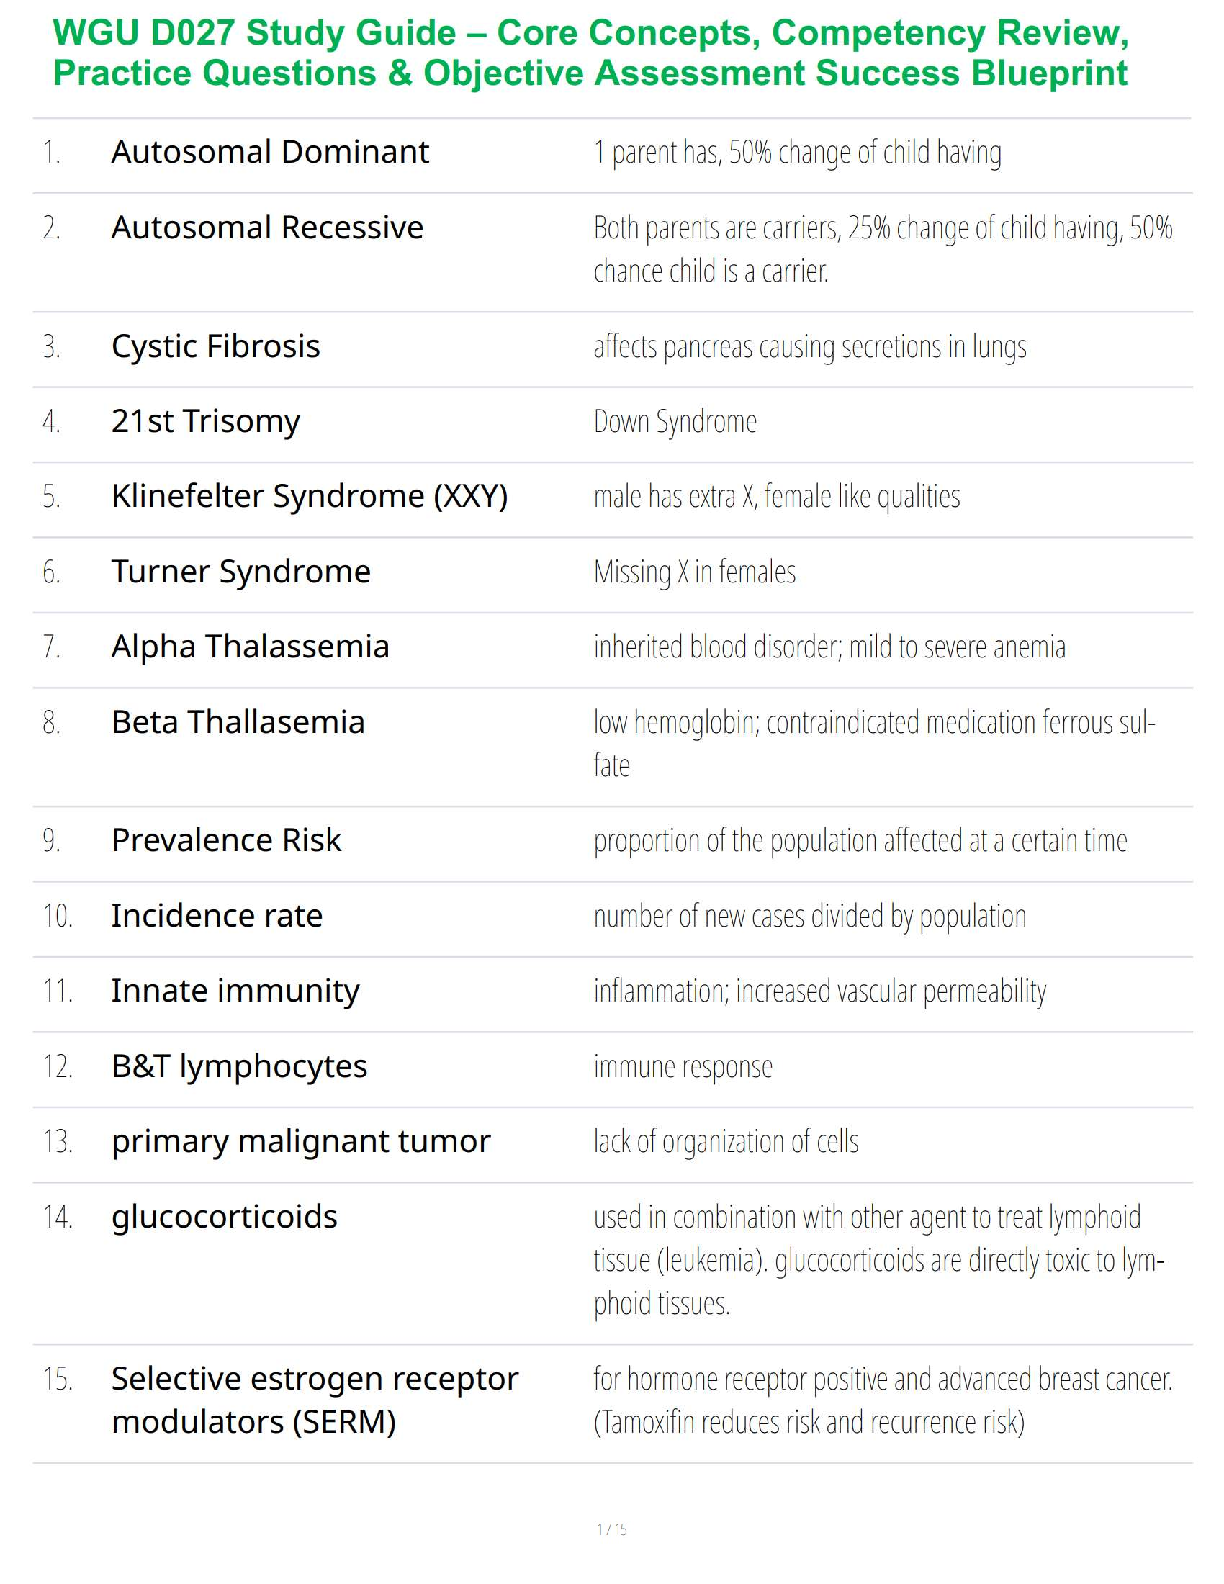
Autosomal Dominant - ✔✔-1 parent has, 50% change of child having
Autosomal Recessive - ✔✔-Both parents are carriers, 25% change of child having, 50% chance child is a
carrier.
Cystic Fibrosis - ✔✔-affects pancreas ca
...
Autosomal Dominant - ✔✔-1 parent has, 50% change of child having
Autosomal Recessive - ✔✔-Both parents are carriers, 25% change of child having, 50% chance child is a
carrier.
Cystic Fibrosis - ✔✔-affects pancreas causing secretions in lungs
21st Trisomy - ✔✔-Down Syndrome
Klinefelter Syndrome (XXY) - ✔✔-male has extra X, female like qualities
Turner Syndrome - ✔✔-Missing X in females
Alpha Thalassemia - ✔✔-inherited blood disorder; mild to severe anemia
Beta Thallasemia - ✔✔-low hemoglobin; contraindicated medication ferrous sulfate
Prevalence Risk - ✔✔-proportion of the population affected at a certain time
Incidence rate - ✔✔-number of new cases divided by population
Innate immunity - ✔✔-inflammation; increased vascular permeability
B&T lymphocytes - ✔✔-immune response
primary malignant tumor - ✔✔-lack of organization of cells
glucocorticoids - ✔✔-used in combination with other agent to treat lymphoid tissue (leukemia).
glucocorticoids are directly toxic to lymphoid tissues.
Selective estrogen receptor modulators (SERM) - ✔✔-for hormone receptor positive and advanced
breast cancer. (Tamoxifin reduces risk and recurrence risk)
Heart failure - ✔✔-impairment of the ventricle to fill with or eject blood; heart cannot meet metabolic
need of the body.
CHF - ✔✔-heart cannot keep up with metabolic needs; volume overload in pulmonary area
Left Ventricular Dysfunction - ✔✔-reduced ejection fraction; ventricle having issue ejecting blood.
normal ejection fraction - ✔✔-55 - 60 % (blood pumped out with each heartbeat)
Ejection fraction of 50% - reduced or preserved? - ✔✔-preserved
Diastolic CHF - ✔✔-preserved ejection fraction, problem is with filling
Systolic CHF - ✔✔-reduced ejection fraction, problem is with ejecting
Left sided CHF - ✔✔-pulmonary (JVD, fluid volume overload, rails, S-3 murmurs) ** #1 cause of Right
sided CHF
BNP - ✔✔-gold standard lab test to diagnose CHF
Echocardiogram - ✔✔-Diagnostic tool, evaluates heart structure and function
At Risk for HF - Stage A - ✔✔-no structural heart disease or symptoms of heart failure
Stage A HF co-morbidities - ✔✔-htn, atherosclerotic disease, diabetes, metabolic syndrome, patients
using cardiotoxins with family history
Therapy goals of stage A HF - ✔✔-treat htn, encourage smoking cessation, encourage regular exercise,
treat lipid disorders, discourage alcohol intake/drug use, control metabolic syndrome
Meds: ACEI or Angiotensin II RB for vascular disease or diabetes (avapro, losartan, benicar, diovan, etc)
At Risk for HF - Stage B - ✔✔-structural heart disease but no symptoms of heart failure
Stage B HF co-morbidities - ✔✔-previous MI, LV remodeling with LV hypertrophy and low EF,
asymptomatic valvular disease
Therapy goals of Stage B HF - ✔✔-Meds: ACEI or ARB, Beta-blockers, inplantable defibrillators
Stage C heart failure - ✔✔-structural heart disease with prior or current symptoms of HF
Presentation of Stage C HF - ✔✔-known structural heart disease and shortness of breath and fatigue,
reduced exercise tolerance
Therapy for Stage C HF - ✔✔-dietary salt restriction, MEDS: diuretic, ACEI, beta blockers. Some patients:
aldosterone antagonist, ARBs, digitalis, hydralazine/nitrates, biventricular pacing, inplantable
defibrillators
Stage D heart failure - ✔✔-refractory HF requiring specialized interventions
Presentation of Stage D HF - ✔✔-marked symptoms at rest despite maximal medical therapy
(recurrently hospitalized or cannot be safely discharged without specialized interventions)
Therapy goals for Stage D HF - ✔✔-compassionate end-of-life care/hospice, extraordinary measures
,heart transplant, chronic inotropes, permanent mechanical support, experimental drugs or surgery
Ischemic heart Disease (CAD, MI) presentation - ✔✔-chest discomfort, pain in neck/jaw/chest (crushing,
squeezing, sharp), pain worse with exertion (demand requirement is higher), abnormal heart sounds,
hypoxia, arrhythmias (afib, ST elevation)
Stable angina goal - ✔✔-decrease cardiac oxygen demand
Meds for stable angina - ✔✔-nitro first choice, then beta blockers (beta blockers if angina occurs with
effort)
nitroglycerine dose - ✔✔-sublingual, acts within 5 minutes, max of 3 doses
Cardiac glycosides (Digoxin) - ✔✔-Increased myocardial contractile force (increases output), used in ED,
exerts positive inotropic action, can cause severe dysrhythmias
Digoxin Dosing - ✔✔-therapeutic - 0.5-0.8 ng/ml. ASSESS apical pulse before administering, If lethargic
and not acting right, see patient FIRST
Goal of Anticoagulant and Antiplatelet Drugs - ✔✔-inactivate and suppress formation of thrombin
Warfarin (coumadin) - ✔✔-PO to prevent blood clots; start with half a dose
Anticoagulants - ✔✔-Warfarin, heparin, lovenox; Caution about hemorrhage, any patients with risks for
bleeding
Pneumonia Patho - ✔✔-pathogen reaches airway and overwhelms defenses causing inflammatory
cascade; fluid forms, blocking diffusion (gas exchange) causing hypoxia, ultimately leads to respiratory
failure
Diagnosing pneumonia - ✔✔-Chest X-ray: viral - diffuse widespread whitening; bacterial - patchy,
consolidated, lobar
Emphysema - ✔✔-destruction of alveolar walls; air goes into lungs, can't get out; leads to hyperinflation
Bronchitis - ✔✔-excess mucus production, smooth muscle hypertrophy
asthma - ✔✔-chronic inflammatory obstruction of bronchi; trigger causing mucus clogging bronchial
tubes; is reversable, give beta antagonists and steroids
Foundation meds of asthma and COPD - ✔✔-glucocorticosteroids: Pulmicort and Flovent; taken daily for
long term control to suppress inflammation.
Oral glucocorticoids - methylprednisone, prednisone; gradually decrease dose
Bronchodilators (Beta 2-Adrenergic Agonists) - ✔✔-provide symptomatic relief, do not effect
inflammation of disease process; taken PRN during attack (Albuterol), long actinb Beta2 can be used in
combo with glucocorticoids
Back pain treatment - ✔✔-first 4-6 weeks no imaging needed unless neurologic involved; give NSAIDS
and rest, is the #1/2 reason for visits to PCP
Types of Endocrine Disorders - ✔✔-Diabetes
Acromegaly - overproduction of growth hormone, have overbite and buffalo hump
Addison's - decreased production of hormones by adrenal gland
Cushing - high cortisol levels
Graves - hyperthyroidism (excessive)
Stage 1 Kidney Disease (CKD) - ✔✔-kidney damage with normal or increased GFR, treat comorbid
conditions to slow disease progression, CVD risk reduction
Stage 2 CKD - ✔✔-kidney damage with mild decreased GFR (60-89), Estimation of progression
Stage 3 CKD - ✔✔-moderate decreased GFR (30-59), treat complications
Stage 4 CKD - ✔✔-Severely decreased GFR (15-29), prepare for kidney replacement therapy
Stage 5 CKD - ✔✔-Kidney failure
GFR <15 or dialysis, replacement if uremia present
How do you start first dose of antihypertensives/heart failure medications? - ✔✔-start first dose at
night; do slow position changes, lay down if hypotension occurs
Ace Inhibiters (ACEI) *pril - ✔✔-reduce angiotensin II, increase bradykinin, hyperkalemia, dry cough,
angioedema; contraindicated in pregnancy (fetal death), first dose causes severe hypotension, can cause
renal failure
Beta Blockers - ✔✔-prevent chemical messengers; slow HR, relax vessels, lower BP, Class II
antidysrhythmic drug
nonselective beta blockers - ✔✔-use with caution in people with lung conditions; do not use with
asthma
Cardio selective beta blockers - ✔✔-metoprolol - only beta-1 receptors affected
Third generation beta blockers - ✔✔-labetalol - blocks alpha and beta receptors
Calcium Channel Blockers - ✔✔-vasodilation of arterioles and heart, class IV antidysrhythmic drug
Verapamil - ✔✔-calcium channel blocker, first choice
dihydropyridines CCB - ✔✔-*ine, vasodilators used to treat htn and angina
non-dihydropyridines CCB - ✔✔-*dilt, used for arrhythmias
Statins - ✔✔-lipid lowering agents (LDL), can increase good HDL, muscle pain can lead to rhabdo, kidney
failure, and death
Diuretics - ✔✔-2 hours after oral intake, peaks at 4-6 hours, lasts 12 hours
Thiazide Diuretics - ✔✔-block reabsorption (10%) in distal convoluted tubule; not used in kidney failure,
can cause hypokalemia, not used in sickle cell disease
Loop diuretics - ✔✔-Furosemide; blocks reabsorption (20%) in loop of Henle
Potassium-sparing diuretics - ✔✔-Spironolactone (Aldactone); distal nephron, holds K, excretes sodium,
takes 48 hours to work
Angiotensin II - ✔✔-vasocontraction; increased bp by acting on adrenal cortex secreting aldosterone
Antiotensin II Receptor Blockers (ARBS) - ✔✔-Sartan; blocks action of angiotensin II, second choice if
cannot tolerate ACE for htn and HF
Diabetes diagnosis - ✔✔-Hgb A1C is most reliable assessment of blood glucose over 3 month period.
Poor control is >9%, goal is <6.5% in healthy people
Short acting insulin - ✔✔-lispro (Humalog)/Aspart (NovoLog)/glulisine (aspirdra)
Long acting insulin - ✔✔-glargine (Lantus) - most painful; detemir (levemir)
Metformin - ✔✔-first drug of choice with new Type 2 Diabetes; inhibits glucose in liver, slightly reduces
glycose absorption in gut, increases glucose uptake; DOES NOT drive insulin down, very low risk for
hypoglycemia
TSH levels - ✔✔-normal range is 0.4 to 4.0 mu/L. If you are being treated for a thyroid disorder, the
normal range is 0.5 to 3.0 mu/L. A value above the normal range indicates that the thyroid is
underactive. This indicates hypothyroidism.
[Show More]




.png)



.png)
.png)