NURSE-UN 240 AE1- Exam 2 Week 5 Latest updated 2022
• Fluid regulation important in maintaining homeostasis
o Influenced by various body systems
▪ Cardiac
▪ GI
▪ Pulmonary
▪ Pituitary
▪ Renal
• Fluid compartments
...
NURSE-UN 240 AE1- Exam 2 Week 5 Latest updated 2022
• Fluid regulation important in maintaining homeostasis
o Influenced by various body systems
▪ Cardiac
▪ GI
▪ Pulmonary
▪ Pituitary
▪ Renal
• Fluid compartments
o Extracellular – 1/3
▪ Interstitial, intravascular
o Intracellular – 2/3
• Hydrostatic = pushing force
o Osmotic = pulling force
• Edema – accumulation of or excess fluid in interstitial space
o Develops with changes in normal hydrostatic pressure differences
• Average daily fluid intake 2300-2600 mL
• Abnormal fluid output – vomiting, wound drainage, hemorrhage
• Aldosterone – secreted by adrenal cortex when extracellular sodium levels are low
o Prevents both water and sodium loss nephrons reabsorb them form urine
• ADH (vasopressin) – secreted by posterior pituitary in response to changes in blood osmolarity
o Water is returned to blood circulation, decreased water secretion
• Natriuretic peptides (ANP) – secreted by cells lining atria and ventricles of heart in response to stretch of heart tissue due to increased blood volume and BP
o Filtration increased to produce more urine
• RAAS
o Renin released by kidneys due to decreased BV going to kidneys converts angiotensinogen (from liver) to angiotensin 1 ACE (secreted by lungs) converts it to angiotensin 2 leads to
▪ Vasoconstriction increase BP
▪ Aldosterone secretion increases sodium and water reabsorption increase BV and BP
▪ ADH secretion further increases water reabsorption
increase BV and BP
• Weight change of 1 lb = fluid volume change of about 500 mL
Electrolyte imbalances
• Sodium – 135-145 mmol/L (neurological)
o Hyponatremia:
▪ Causes: sodium loss (vomiting, diarrhea, diuretic use) or sodium dilution (inappropriate administration of hypotonic IVF)
▪ Signs and symptoms:
• Neurologic issues sudden onset of acute confusion, increased confusion
• Seizures
• Neuromuscular changes general muscle weakness, decreased deep tendon reflex
• Cardiovascular
• Dependent on type:
o Hypovolemia – signs and symptoms of
dehydration
o Hypervolemia – signs and symptoms of fluid overload
o Hypernatremia:
▪ Causes: increased intake, inappropriate administration of IVFs that contain sodium, corticosteroids, hyperaldosteronism, Cushing syndrome
▪ Signs and symptoms
• Short attention span and confusion
• Lethargic, drowsy
• Skeletal muscle muscle twitching and irregular muscle contractions
• Cardiovascular impaired cardiac function due to decreased contractility
• Potassium – 3.5-5.0 (cardiac)
o Control over intracellular osmolarity and volume
o Regulate protein synthesis, glucose use and storage
o Hypokalemia:
▪ Skeletal muscle weakness, thready and weak pulse
o Hyperkalemia:
▪ EKG changes, increase GI motility, parenthesis (pins and needles, tingling)
• Calcium – 9.0-11.0 (skeletal)
o Stored in bones
o Absorption requires active form of vitamin D
o Hypocalcemia:
▪ Muscle spasm, positive Trosseau (arm) and Chvostek (face) signs
o Hypercalcemia:
▪ Mild – increase heart rate and BP
▪ Severe – depressed cardiac conduction and slowed heart rate
• Phosphorus – 2.5-4.5
o Found in bones
o Activates vitamins and enzymes, assists in cell growth and metabolism
o Plasma levels of calcium and phosphorus balanced reciprocal relationship
o Hypophosphatemia:
▪ Decreased cell membrane excitability
o Hyperphosphatemia:
▪ Increased cell membrane excitability
• Magnesium – 1.5-2.5
o Critical for skeletal muscle contraction, carbohydrate metabolism, ATP
formation, vitamin activation, cell growth
o Hypomagnesemia
▪ Increased cell membrane excitability
o Hypermagnesemia
▪ Decreased cell membrane excitability
• Chloride – 96-106
o Imbalance occurs as result of other electrolyte imbalances
▪ Especially sodium hyponatremia most like = hypochloremia
o Treat underlying electrolyte imbalance or acid-base problem
• Older adults are more at risk for electrolyte imbalances
o Age-related organ changes
o Have less total body water
• Lungs excrete carbonic acid
o Kidney excrete all other acids
• Nursing assessment
o Age: very young and old at risk
o Environment: excessively hot?
o Dietary intake: fluids, salt, foods rich in potassium, calcium, and magnesium
o Lifestyle: alcohol intake history
o Medications: include over-the-counter (OTC) and herbal, in addition to prescription medications
• Anesthesia slows down peristalsis and urine output
• Enteral – by mouth
• Parenteral – by IV (anything that isnt by mouth)
o TPN total parenteral nutrition
o Crytalloids – small enough to pass through membrane
o Colloids – too big to do so
• Types of IVF solutions – described by tonicity in relation to plasma
o Isotonic: 0.9% NaCl (normal saline), lactated ringer’s
o Hypotonic: 0.45% NaCl (half normal saline), 0.33% NaCl
o Hypertonic: 3% NaCl, Dextrose 10% in water (D10W)
▪ Osmotic diuretic – reduces increased intracranial pressure (cerebral swelling or meningitis)
• Not all patients require IV fluids – important to get an IV started in all patients just in case of an emergency where later on will need to push fluids
• Select most distal sight of non-dominant hand for insertion (if possible)
o Increases potential sites for other IVs if needed
• Complications:
o Fluid overload – dyspnea, shortness of breath, crackles
o Infiltration – leakage of non-vesicant (doesn’t irritate tissue) fluid into extravascular tissue
▪ Edema, cool to touch, blanching at site
o Extravasation – leakage of IV fluids or medications into extravascular
tissue around infusion site (vesicant – irritates tissues)
▪ Can cause damage to tissues
o Phlebitis – inflammation of the vein
▪ Warm sensation, erythema
• Peripheral catheters – short term use (fluid restoration after surgery, short- term antibiotic administration)
• Central catheters and implanted ports – catheters or infusion ports designed for repeated access to vascular system
o Long term use – empty into central vein (bigger vessel)
o Ex: PICC lines, triple lumen central catheters
o At jugular area not usually permanent – cant go home with them
Week 6
• Nociceptive pain – somatic or visceral
• Neuropathic pain – no physical evidence of damage
o Nerve pain
• Painful stimuli often originate in extremities
o If pain not transmitted to brain – person feels no pain
• Two specific fibers transmit periphery pain
o A delta fibers – myelinated fast conduction
o C fibers – unmyelinated
• Gate-control theory – allows for non-pharmacological interventions to work (ex: massage, ice, acupuncture)
o Other nerve fibers conduct and inhibit/block pain stimuli towards the brain
• Body can self modulate pain perception release of endorphins, endogenous opioids
• Patients who cant self-report pain are at highest risk for undertreated pain
o Checklist of nonverbal pain indicators (CNPI)
o Pain assessment in advanced dementia scale (PA11/4/20AD)
• Pain management:
o Analgesic agents (pain killers) – first line therapy
o Multimodal analgesia (multiple types) – preemptive analgesia (before procedure/pain causing agent)
o Multiple routes
o Around-the-clock dosing
o Patient controlled analgesia (PCA)
• Analgesics
o Acetaminophen (Tylenol, Abenol, Advil)
o NSAIDS
▪ Ibuprofen (Motrin, Novo-Profen)
▪ Naproxen (Naprosyn, Nu-Naprox, Aleeve)
▪ Celecoxib (Celebrex)
• Opioid analgesics
o Full or mu agonists – morphine, fentanyl, hydromorphone, oxycodone, hydrocodone
o Mixed agonists antagonists – butorphanol, nalbuphine
o Partial agonists – buprenorphine
• Adjuvant medication – not primarily designed to control pain but can be used for analgesic purpose
• Side effects of opioids
o Constipation
o Nausea
o Vomiting
o Pruritus
o Sedation
o Respiratory depression (less common, most feared)
▪ Narcan (Naloxone) can reverse effect
• Physical dependence – normal response after repeated given doses after days
o Quick withdrawal will cause biological symptoms
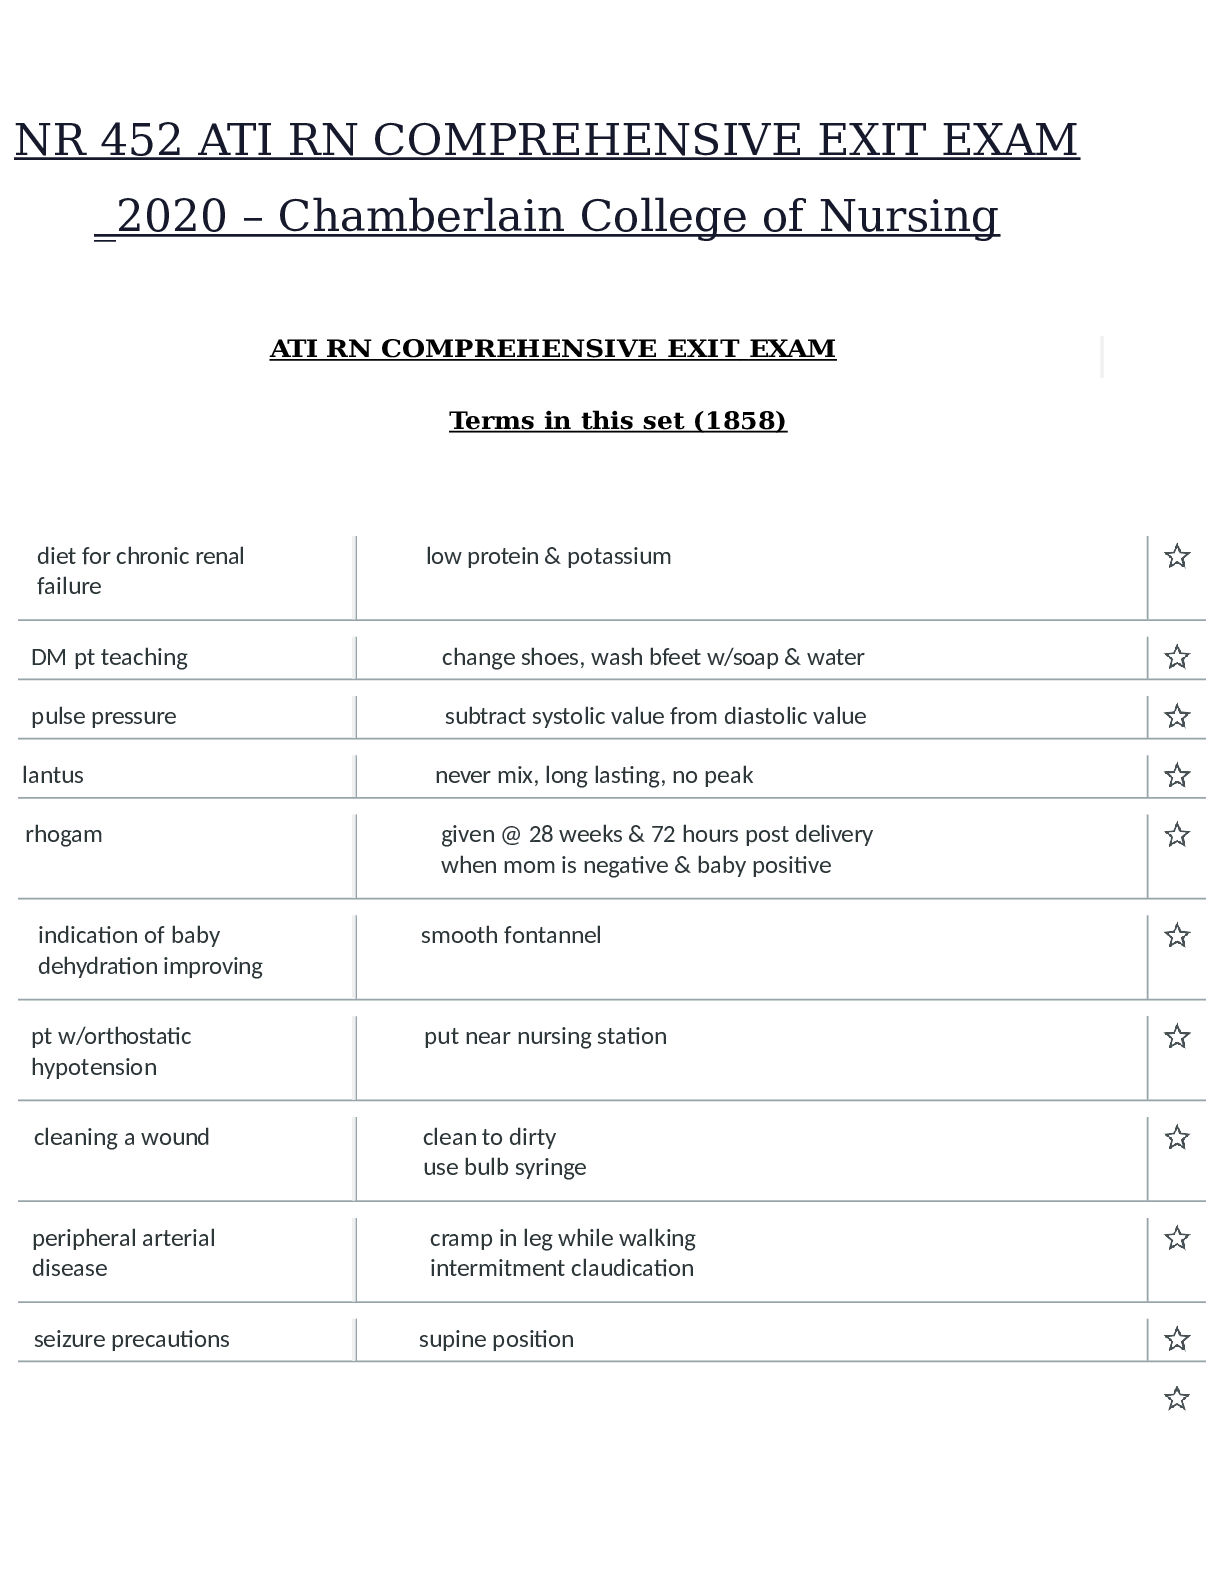
• Tolerance – decrease in effect leading to need increase dose (normal response)
• Opioid addiction – chronic neurologic and biologic disease
o Impaired control, compulsive use, continued use after no longer needing it
• Pseudoaddiction – mistaken diagnosis of addictive disease
o Patient asking for more medications after not receiving adequate pain relief
• Opioid use in older adults start with low doses and slowly titrate
• Sleep is regulated by a sequence of physiological states integrated by CNS activity
o Hypothalamus
o Reticular activating system (RAS)
• Sleep = homeostatic process
• Stages of adult sleep cycle
o 4 stages of NREM
o Sleep cycle lasts 90-100 minutes
▪ REM lasts 60 mins
o Sleep goes through stages 1-4 then reversal from 4-2 followed by REM
o REM – important for memory consolidation and is period when most vivid dreams occur
• Hypothalamus = major sleep control center
o Promotes wakefulness and REM through hormones
• Purpose of sleep still remains unclear
o Physiological and psychological restoration
o Maintenance of biological functions
o Circadian rhythms
▪ Affected by light, temperature, social activities and work routines
• Dreams are important for learning, memory and adaptation to stress
• Sleep disorders:
o Insomnia – adjustment sleep disorder (acute insomnia)
▪ Inadequate sleep hygiene, behavioral insomnia of childhood, insomnia caused by medical condition
▪ Difficulty falling asleep and staying asleep overall disappointment of quantity and quality of sleep
o Sleep apnea – primary central sleep apnea, central sleep apnea caused by medical condition, obstructive sleep apnea syndromes
▪ Daytime sleepiness, loud snoring, wake up feeling unrested
o Narcolepsy – cataplexy (brief and sudden loss of voluntary muscle tone triggered by strong emotions), sleep paralysis
▪ Dysfunction in sleep and wake cycle
▪ Not cured but can have medication
▪ Go into REM within 15 mins
o Sleep deprivation – emotional distress, medications, environmental disturbances
o Parasomnias – somnambulism (sleep walking), night terrors, nightmares, nocturnal enuresis (bed-wetting), body rocking, bruxism (grinding teeth)
• Factors influencing sleep
o Drugs and substances – hypnotics, diuretics, narcotics, antidepressants, alcohol, caffeine, beta-blockers, anticonvulsants
o Lifestyle – work schedule, social activities, routines
o Usual sleep patters – may be disrupted by social activities or work schedule
o Environment – noise, routines, good ventilation
▪ Not sleeping with someone that you’re used to sleeping with
o Emotional stress – worries, physical health, death, losses
o Exercise and fatigue – moderate exercise and fatigue can cause a restful sleep
o Food and calorie intake – time of day, caffeine, nicotine, alcohol
▪ Glucose increase (surge) insulin rushes in cell and lowers blood glucose which causes being sleeping after big meal or lots of candy
▪ Full meal before bed time interrupts sleep – GI upset
• Pharmacological approaches to sleep melatonin, chamomile, non- prescription drugs, valerian
• Endorphins released during strenuous exercise will interrupt sleep
Week 7
• Ventilation – movement of air in and out of lungs
• Perfusion – ability of cardiovascular system to pump oxygenated blood to tissues
• Diffusion – exchange of respiratory gasses in alveoli and capillaries
• CO = SV x HR
o CO volume of blood pumped each minute
o SV amount of blood pumped each heart beat
• Frank’s sterling law/curve – chamber performance dictates volume
o Stretch of myocardium in relation to amount of blood in it –
determines pressure blood will move on into next chamber
• When afterload is increased for too long cardiac issues (hypertrophy)
o CO + SV determined by afterload
o SV determined by preload + afterload
• Impulses traveling through heart – determine contractions
o SA node AV node Bundle of His right + left bundle branches
purkinje fibers
• Altered cardiac functioning:
o Disturbances in conduction (ex: arrhythmias, dysrhythmias)
o Altered cardiac output (ex: heart failure: left sided, right sided, bi- ventricular)
o Impaired valvular function (ex: valvular stenosis)
o Myocardial ischemia (ex: angina, myocardial infarctions or acute coronary syndrome)
• Normal sinus rhythm: depolarization = contraction, repolarization = relaxation
o P wave atrial contraction
o PR interval time between beginning of atrial contraction and ventricular contraction
o QRS ventricular contraction
o T wave ventricular relaxation
o QT interval time between beginning of ventricular contraction and end of ventricular relaxation
Relaxation of atria not shown because conduction is so small
• Early vs late sings of hypoxia
o Early: BP elevated unless patient is in shock
o Late: RR decreases, patient is cyanotic
• Diagnostic studies:
o X-ray
o Common blood tests:
▪ CBC/Hemogram
▪ Cardiac enzymes
▪ Serum electrolytes
▪ Cholesterol
o Bronchoscopy
o Lung CT Scan
o O2 Sat
o Thoracentesis – insertion of pleural effusion needle in pleural space to remove excess fluid
o TB testing
o Sputum test
o ECG
• Normal values for CBC
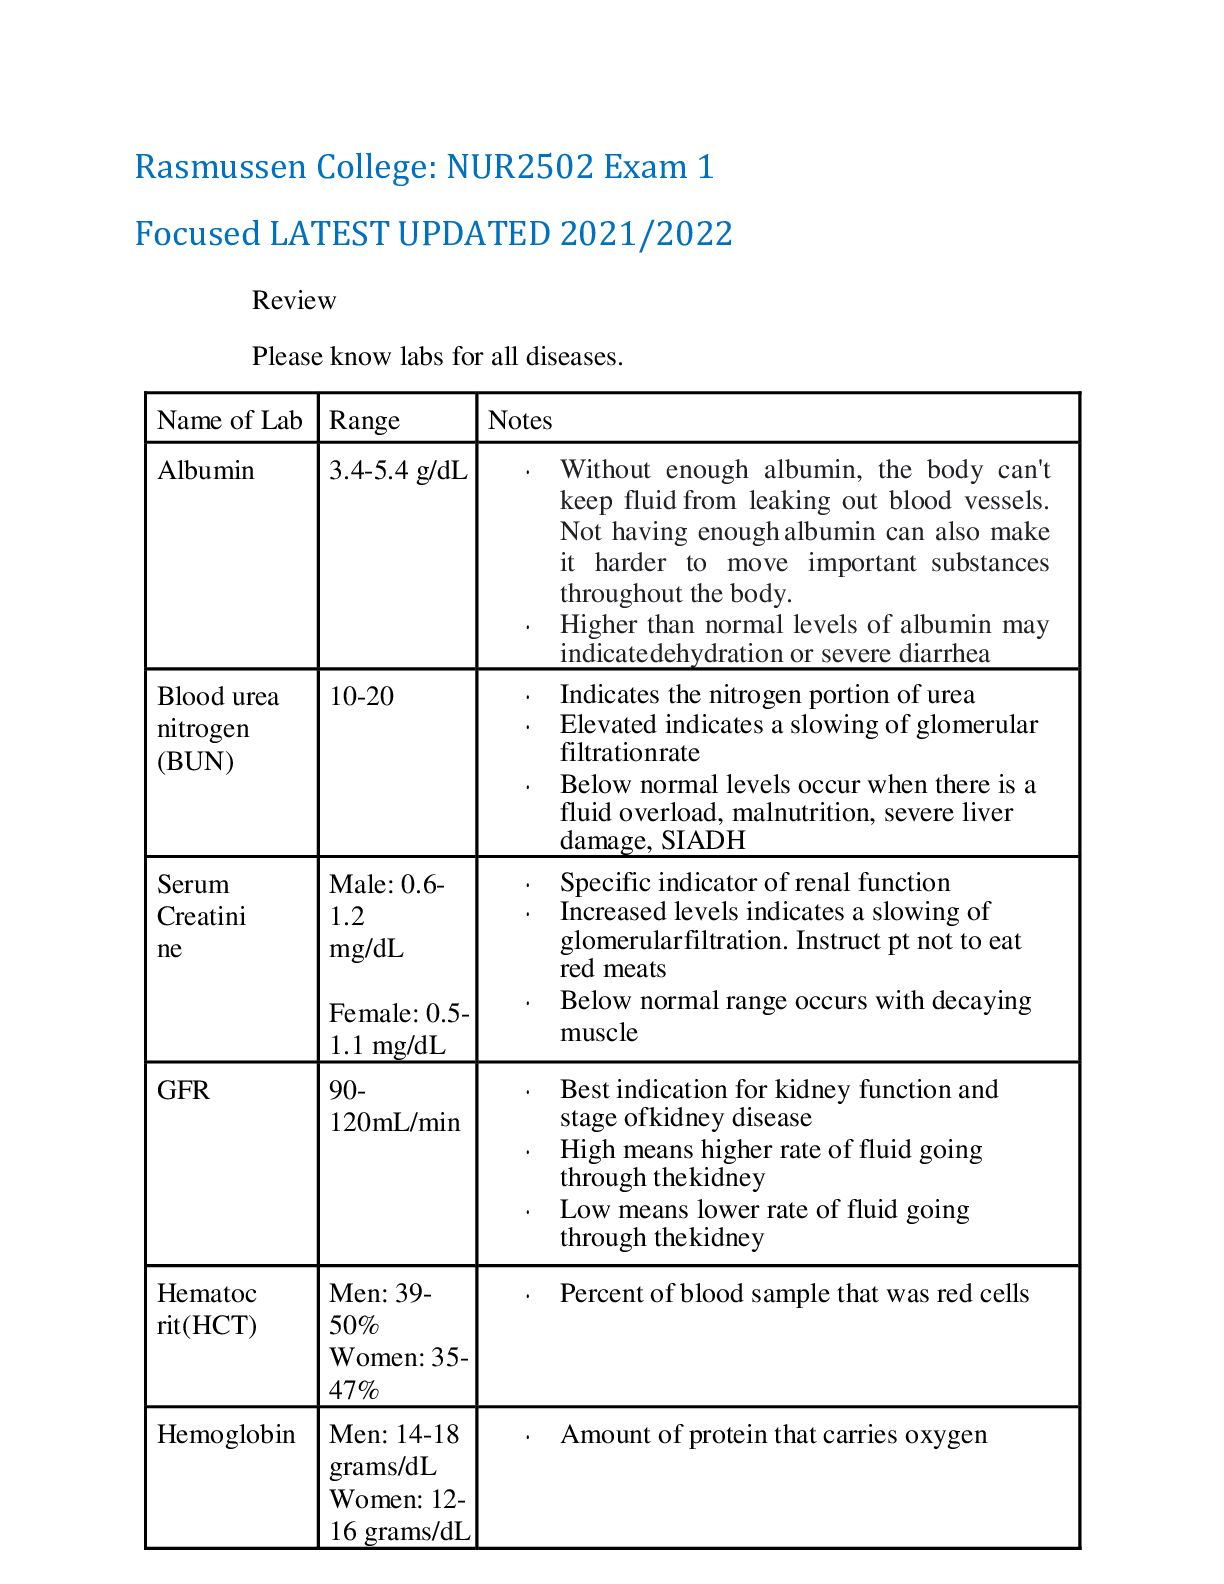
o Hemoglobin (g/dL): Male: 13.5 – 16.5; Female: 12.0 – 15.0
o Hematocrit (%): Male: 41 – 50; Female: 36 – 44
o Red blood cell count (x106 cells/ml): 4.5 – 5.5
o White blood cell count (cells/mL): 4,500 – 11,000
o Platelets (platelets/µL): 150,000 – 400,000
• Cardiac enzymes – cardiac muscles release enzymes when injured
o Troponin – elevates as early as 3 hours after myocardial injury
▪ Stays elevated for 7-10 days
▪ I: <0.03ng/mL, T: <0.1ng/mL
o Creatine Kinase (CK) – peaks 12-24 hours after chest pain
▪ Male: 55-170units/L, female: 30-135units/L
o Myoglobin – early index of damage to myocardium in MI or
reinfarction
▪ Increases within 3 hours
▪ < 90mcg/L
• Patients on diuretic therapy – risk for hypokalemia
o Patients on ACE inhibitors – risk for hyperkalemia
• Cholesterol normal values:
o Fasting cholesterol less than 200 mg/dL
o Low-density lipoproteins (LDLs; “bad” cholesterol) < 100 mg/dL
o Very low–density lipoproteins (VLDLs) 7-32 mg/dl
o High-density lipoproteins (HDLs; “good” cholesterol)
▪ Male: > 40 mg/dL
▪ Female: > 50 mg/dL
o Triglycerides
▪ < 160 mg/dL
• Meter-dose inhalers: deliver controlled does of medication with each compression of canister
• Dry powder inhalers: breath-activated delivery of medications
• Live, attenuated nasal spray flu vaccine not for older adults
• Pneumococcal vaccine – every 5 years for those over 65
o Especially for those living in long term care institutions
• Emphysema:
o Dyspnea
o Minimal cough
o Pink skin – still oxygenating and are pink because theyre breathing so fast
o Pursed lip breathing
o Accessory muscle use
o Cachexia
o Barrel chest
o Decreased breath sounds
o Hyperinflation
• Chronic bronchitis:
o Chronic cough
o Purulent sputum
o Hemopytosis
o Mild dyspnea
o Cyanosis (hypoxemia)
o Peripheral edema (cor pulmonale)
o Crackles/wheezes
o Prolonged expiration
o Obese
• Nicotine acts as stimulants to SNS – increased HR, peripheral vasoconstriction, increased BP and cardiac workload
o Decreased ciliary activity
o Mucous production
o Increased difficulty in clearing secretions
• COPD patients may appear thin or have unplanned weight loss – use of nutrient stores to breathe
• Alpha-1 AntiTrypsin deficiency – allows proteolytic enzymes to deteriorate alveoli
o Enzyme gets rid of proteolytic enzymes surrounding alveoli
Week 8
• Diabetes mellitus – group of metabolic diseases characterized by hyperglycemia resulting from abnormal insulin production, impaired insulin use or both
o Involves improper metabolism of carbs, fats and proteins
• Chronic hyperglycemia associated with long-term damage, dysfunction and failure of various organs
o Eyes, kidneys, nerves, heart and blood vessels
• Gestational diabetes – body cant make enough insulin and use it less effectively (insulin resistance)
o Around 24 weeks
• Type 1 antibodies present for months to years before symptoms occur and manifestations develop when pancreas can no longer produce insulin – then rapid onset with ketoacidosis
o Age: any age but more common in young people
o Type: abrupt onset but may have been present for many years
o Prevalence: 5-10%
o Environmental factors: virus, toxins
o Primary defect: absent of minimal insulin production
o Islet cell antibodies: present at onset
▪ Autoimmune/ genetic condition: patient will develop antibodies to insulin producing cells
Kasoki virus and mumps are associated with it
• Type 2 hyperglycemia may go many years without being detected, many times discovered with routine laboratory testing
o Age: adults, incidence increasing in children
o Type: insidious
o Prevalence: 90-95%
o Environmental factors: obesity, lack of exercise
o Primary defect: insulin resistance, decreased production, altered adopokines
o Islet cell antibodies: absent
• Metabolic syndrome increases risk for type 2 diabetes 3/5 risk factors indicates metabolic syndrome
o Elevated glucose levels
o Abdominal obesity
o Elevated BP
o High levels of triglycerides
o Decreased levels of HDLs
• Type 1 clinical manifestations:
o Weight loss – loss of calories and water in urine
o Polydipsia
o Polyuria
o Polyphagia
• Type 2 clinical manifestations: can also present with 3 Ps
o Non-specific symptoms
o Fatigue
o Recurrent infections
o Prolonged wound healing
o Visual changes
• Criteria for diagnosis – to actually diagnose need to repeat test and confirm diagnosis
o Fasting plasma glucose ≥ 126 mg/dL
▪ Fasting = no caloric intake for ≥ 8 hours
o 2-hr PG ≥ 200 mg/dL during OGTT (75g)
▪ Using glucose load containing equivalent of 75g anhydrous glucose dissolved in water
o A1C ≥ 6.5%
▪ Reflects past 60-90 days
▪ Normal: reduces risk of retinopathy, neuropathy, and nephropathy
o Random PG ≥ 200 mg/dL
▪ In individuals with symptoms of hyperglycemia or hyperglycemic crisis
• Pre-diabetes: FPG 100-125 mg/dL
o Known as impaired glucose tolerance or impaired fasting glucose
o 2 hour PG higher than normal (140-199 mg/dL)
o A1C – 5.7-6.4%
o If no preventative measures taken – can develop within 10 years
▪ Leads to microvascular and macrovascular changes
• Hypoglycemia (BG ≤ 70 mg/dL)
o Causes
▪ Receiving too much insulin
▪ Decreased food intake
▪ Exercise
▪ Alcohol intake
o Manifestations
▪ Confusion/irritability
▪ Diaphoresis
▪ Tremors
▪ Hunger
▪ Weakness and visual disturbances
▪ Can mimic intoxication
▪ Untreated can progress loss of consciousness, seizures, coma, and death
o Treatment: rule of 15 (if alert to swallow)
▪ 15-20 grams of simple carbs
▪ Recheck BG 15 minutes after treatment
▪ Repeat until BG is above 70
▪ Patient should eat regularly scheduled meal/snack to prevent rebound hypoglycemia
▪ Check BG again 45-60 minutes after treatment
o Treatment: severe BG ≤ 20 or no improvement after 2-3 doses of
simple carbs or not alert enough to swallow
▪ Administer 1 mg of glucagon IM or subcutaneously
• Aids in producing/stimulating hepatic glucose production increases BG levels
• Side effect: rebound hyperglycemia
▪ 50% dextrose IV push
▪ Have patient ingest complex carb after recovery
• Hyperglycemia (BG ≥ 200 mg/dL)
o Causes
▪ Stress
▪ Medications (steroids)
▪ Not taking insulin
▪ Extra sugar intake
o Complications:
▪ Type 1: Diabetic Ketoacidosis (DKA) BG ≥ 250 mg/dL metabolic acidotic state
• Positive ketones in blood and urine
• Kussmaul’s respirations
• “Fruity” breath
• Nausea and abdominal pain
• Clinical manifestations of dehydration
• Treatment: ensure patent airway, administer O2, establish IV access and begin fluid resuscitation, protect
from cerebral edema, monitor for fluid overload
▪ Type 2: Hyperglycemic hyperosmolar state (HHS) BG ≥ 600 mg/dL
• Negative ketones in blood and urine
• Neurologic symptoms
• Clinical manifestations of dehydration
• Treatment: IV insulin and NaCl infusions, fluid replacement, monitor!!!, correct underlying
precipitating cause
o Treatments:
▪ Get medical care
▪ Continue diabetes med as prescribed
▪ Check BG and urine ketones
▪ Drink fluids hourly
▪ Contact HCP with ketonuria
• Chronic complications:
o Retinopathy
o Nephropathy
▪ Males may have erectile dysfunction
▪ Sexual dysfunction
o Neuropathy (foot and lower extremities)
▪ Nervous system disease, amputations, pressure injuries (foot), delayed wound healing call HCP if injury doesn’t begin to heal after 2 days
o Cardiovascular disease
▪ Heart disease, high BP,
o Complications of pregnancy
o Dental disease
• Nutritional therapy
o Carbohydrates
▪ Minimum of 130 g/day
▪ Fruits, vegetables, whole grains, legumes, low-fat milk
▪ Monitor with CHO counting, exchanges, or experienced-based estimation
▪ Use glycemic index
▪ Sucrose-containing food substituted for other CHOs
o Fats
▪ Limit saturated fats to less than 7% of total calories
▪ Limit cholesterol to less than 200 mg/day
▪ Minimize trans fat
• Pharmacology
o Type 1 – insulin
o Type 2 – oral agents (many different classes) and may progress to insulin at some point
• Basal-bolus regimen
o Intensive or physiologic insulin therapy – most closely mimics
endogenous insulin production
o Administer multiple daily injections (or insulin pump) with frequent self monitoring of BG (or continuous glucose monitoring system)
o Bolus – rapid or short acting insulin before meals
o Basal – intermediate or long acting insulin once or twice a day
o Goal: achieve glucose level as close to normal as possible as much of the time as possible
[Show More]




- Test Bank.png)