Chapter 38: Coordinating Care for Patients with Peripheral Nervous System Disorders
The Nervous System
• CNS includes the brain and spinal cord
o oligodendrocytes make the myelin that covers nerve fibers
• PNS=
...
Chapter 38: Coordinating Care for Patients with Peripheral Nervous System Disorders
The Nervous System
• CNS includes the brain and spinal cord
o oligodendrocytes make the myelin that covers nerve fibers
• PNS= sensory and motor divisions
o sensory division includes sensory neurons that are responsible for innervating the skin, muscles, joints, and viscera
o motor division includes the motor neurons that control skeletal muscles and the autonomic nervous system (ANS) that innervates smooth and cardiac muscles and glands
o The PNS is composed of nerves outside the cranium and vertebral column that include cranial and spinal nerves, neuromuscular junctions which are the synapses between the somatic motor neuron’s axon and the muscle, muscles, and the ANS
o In the PNS, the Schwann cells make the myelin that wraps around the nerves
• ANS: regulates involuntary body functions
o Sympathetic: “fight-or-flight system”
o input is received from the thoracic and lumbar regions of the spinal cord
▪ elevates the heart rate (HR) and blood
pressure (BP), increases the respiratory rate (RR), dilates the pupils, shunts blood to the skeletal muscles and skin, and slows digestion
o Parasympathetic
▪ “rest and digest”
• responsible for slowing the HR, lowering the BP, decreasing
respirations, shunting blood from the periphery of the body to the internal organs, constricting the pupils, and digesting food
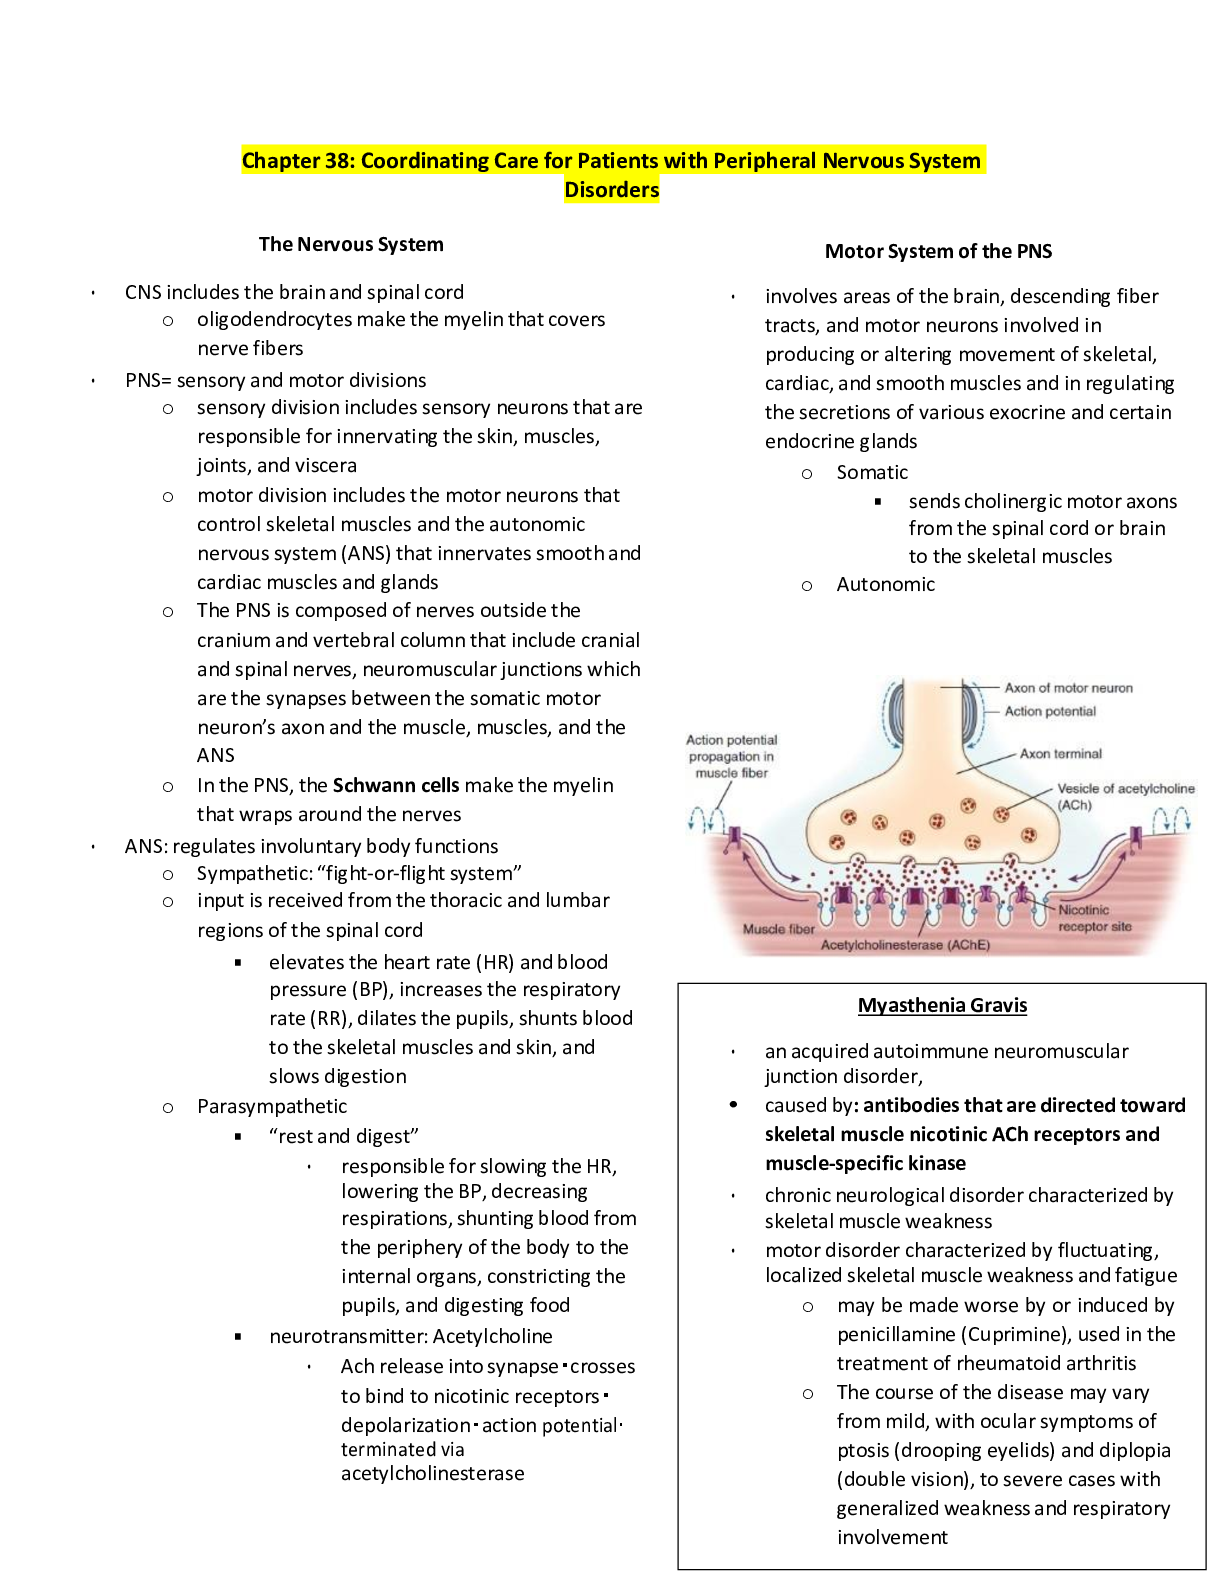
▪ neurotransmitter: Acetylcholine
• Ach release into synapsecrosses to bind to nicotinic receptors depolarizationaction potential terminated via acetylcholinesterase
Motor System of the PNS
• involves areas of the brain, descending fiber tracts, and motor neurons involved in producing or altering movement of skeletal, cardiac, and smooth muscles and in regulating the secretions of various exocrine and certain endocrine glands
o Somatic
▪ sends cholinergic motor axons from the spinal cord or brain to the skeletal muscles
o Autonomic
• Common in women (20 to 30 years); men (60 to 80 years)
• circulating anti-AChR antibodies bind with the
AChR, resulting in complement-mediated destruction of receptor sites
o Postsynaptic membranes lose their folds
o ACh binding is blocked
▪ Resulting in muscle contraction, skeletal muscle weakness and fragility
• there is an adequate amount of ACh released, but postsynaptic receptor sites are not available
• presents as 1 of 3 serotypes: anti-AChR (Found in 80% of patients), MuSK (10%), or seronegative MG (10%)
o 70% of pts. have thymic hyperplasia (enlarged thymus), whereas 10% have thymoma (tumor of the thymus gland)
▪ Patients with thymoma typically
have higher levels of antibodies and a more severe disease course Thymectomy
CN Involvement in MG
CN Function
IX (glossopharyngeal) • Motor fibers control tongue movement, swallowing, and gagging
• Sensory function controls taste, touch, and temperature from the tongue; also has role in blood
pressure control
X (vagus) • Innervates organs in the head, neck, thoracic and abdominal cavities
• Key role in function
XI (spinal accessory) • Controls movement of the head,
neck, and shoulders
XII (hypoglossal) • Controls tongue movement
Clinical Manifestations
• Muscle weakness and fatigue
o muscles of the neck, deltoids, triceps, wrists, fingers, and ankles are commonly affected
• Ocular symptoms
o ptosis and diplopia
• Bulbar symptoms
o symptomatology involving cranial nerves (CN IX, CN X, CN XI, and CN XII) that emerge from the medulla of the brainstemdifficulty with phonation, chewing, and swallowing
Labs and Diagnostic Tests
• Serological Testing: The AChR-binding antibody assay is very specific, and positive antibody studies verify MG in the presence of a clinical picture that is consistent with MG
o MuSK antibodies: found generally in females with bulbar sympotoms, shoulder girdle weakness, and respiratory weakness
• Repetitive Nerve Stimulation and Electromyography:
diagnostic tool used to evaluate neuromuscular transmission, and measures muscle action potential after repeated nerve stimulations
o Single-fiber electromyography: most sensitive diagnostic tool for detecting an abnormality in neuromuscular transmission
▪ requires needles to be placed in the
muscle to measure electrical activity with an increased fluctuations “jitter” (evoked responses from two muscle fibers firing with minimal fluctuation of the interval between the two)
• Tensilon (edrophonium) Test
o Up to 10 mg of edrophonium, a short-acting anticholinesterase medication, is administered IV
Treatments aimed
Medications
push
▪ Edrophonium temporarily improves neuromuscular transmission by inhibiting AChE
o Before the medication is administered, the provider focuses on a weak group of muscles such as the ocular muscles
o An initial dose of 2 mg is given while the patient has sustained visual focus on an object The provider assesses for improvement of the ptosis
o If no effect is observed, additional doses of 3 and 5 mg are administered at 1-minute intervals
o Positive Test: Improvement of muscle weakness at 2 to 5 minutes followed by return to baseline over the next 5 minutes
o Can cause acculumation of Ach and increased stimulation of muscarinic receptors
▪ Side effects: bronchospasm, bradycardia,
and diarrhea
o Atropine: reverse side effects
• CT Scan
o routinely performed to evaluate the patient with MG for thymoma
Medications for MG
1. symptomatic treatment to increase the availability of Ach
2. immunosuppression
3. approaches to alter the immunopathogenic mechanism underlying MG
4. immunomodulary effect with thymectomy
• Pyridostigmine (Mestinon)
o improves neuromuscular transmission by increasing ACh stimulation of the AChRs that are available
o dosage is 30 to 60 mg by mouth every 4 hours while the patient is awake,
o sustained-release formula (180-mg) tablet may be given to the patient at night before sleep
o side effects: stomach cramps, diarrhea, increased secretions, nausea, bradycardia, and muscle twitches
• Neostigmine (Prostigmin)
o Shorter actiong AchE inhibitor
o IV if PO is unavailable
o IV site need to be monitored frequently; dual access
o ratio of IV neostigmine is 1 mg equals 60 mg pyridostigmine
▪ The nurse administers the oral
pyridostigmine 1 hour before stopping the IV drug
o Side effects: bradycardia and cardiac dysrhythmias
• Immunotherapy
o Prednisone
o Azathioprine (Imuran): inhibits T-cell and B- cell proliferation through interaction with purine metabolism and nucleic acid synthesis
o Cyclosporine: inhibits T helper cell–mediated synthesis of cytokines and other T helper cell–mediated immune reactions
▪ used successfully in patients when
steroids and thymectomy have failed
▪ time to treatment response is approximately 7 months
o Mycophenolate mofetil (CellCept): suppresses both T-cell and B-cell proliferation
▪ Dosage: 1 g twice a day
▪ Adverse effects: diarrhea, anemia, leukopenia, and infections
o Cyclophosphamide (Cytoxan): chemo agent
▪ High dosages: destroy BM and allow the patient’s endogenous stem cells to repopulate the immune system with new lymphocytes allows or immune system to “reboot”
• Medications to Be Used With Caution in MG
o Antibiotics (streptomycin and polymyxin)
o calcium channel blockers,
o D-penicillamine
o Magnesium
▪ Be aware of certain antacids and laxatives that also contain magnesium
▪ If any of these medications are
ordered, the nurse should consult with the provider to determine if increased clinical assessments should be performed
Diet
• At risk for aspiration due to trouble chewing or swallowing
o thickened liquids
o enteral tube feedings
Medications Known to Exacerbate Myasthenia Gravis
Class of Meds Names
Antibiotics Aminoglycosides, ciprofloxacin, clindamycin, telithromycin,
ampicillin, erythromycin
Antiarrhythmics Procainamide, propranolol,
timolol, verapamil, quinidine
Neuropsychiatrics Phenytoin, trimethadione,
lithium
Other Trihexyphenidyl, neuromuscular-blocking agents, magnesium preparations, carbamazepine, oral contraceptives, transdermal
nicotine
Additional Therapies
• Intravenous Immunoglobulin: concentrated immunoglobulin (Ig) solution primarily composed of IgG that is produced from pooled blood donors
o inactivates abnormal autoantibodies and suppresses T-cell function
o costly, and a treatment is $10,000
o dose: over 3 to 5 days is 2 g/kg
▪ vitals check frequently; monitor for flu like symptoms (fever, headache, chills, myalgia)
▪ Monitor RFTs (BUN and Creatinine)
▪ Carefully administered in pts. with
Diabetes or renal insufficiency b/c renal failure is a potential complication
• Plasmapheresis: insertion of a large-bore dual-
lumen catheter
o the patient’s blood is removed through the arterial lumen and circulated through the plasmapheresis machine, which removes antibodies that block AChR function.
o Goal of treatment: Improve muscle strength
o Anticoagulant: Citrate is added to blood outside of body to prevent clotting
▪ Citrate can cause hypokalemia
(report: tingling/numbness especially in lips)
o Seven treatments can cause hypotension
o Clotting factors and calcium are removed
o citrate-induced Hypocalcemia prevention: adding calcium to the replacement fluid, 5% albumin, or by slowing down the infusion of the citrate during the procedure
▪ not treated: can progress from
paresthesias, vibration sensation, nausea/vomiting, and diarrhea to hypotension, chest tightness, tetany, and cardiac arrhythmias
o fluid shift occur; may experience N/V and E.Imbalances
o Hypovolemia
▪ S/S: dizziness, light-headedness, nausea, diaphoresis, tachycardia, and hypotension
▪ Treatment: pausing the procedure,
placing the patient in a Trendelenburg position if not contraindicated, and administering a saline bolus of fluids
• In subsequent procedures, replacement fluids may be adjusted with an increase in colloids and a decrease in crystalloids
o vasovagal reaction
▪ S/S: pallor, sweating, diaphoresis, nausea/vomiting, hypotension, and bradycardia
▪ Treatment: same for hypovolemia
o Potassium and Calcium need to be monitored
o The pheresis nurse instills heparin in each port of the dual-lumen catheter following the plasmapheresis treatment
▪ The catheter also needs to be
instilled with heparin on nonpheresis days to prevent clotting
▪ Whenever the catheter is
accessed, the heparin must first be removed before the line is flushed so that the patient does not receive a bolus of heparin
▪ Risk for infection and thrombotic
complications
Surgical Management
• Thymectomy
o performed within the first 3 years of diagnosis and in individuals less than the age of 65
o always performed for patients with thymoma
o standard approach is transsternal extended thymectomy
▪ transcervical and videoendoscopic
procedures, including robotic-assisted surgery, are gaining popularity because of shorter hospital stays and improved cosmetic results
o require IV neostigmine (Prostigmin) because of NPO status and management in an intensive care unit following surgery
▪ IV neostigmine, an IV
anticholinesterase medication, is required to maintain muscle strength and respiratory function
▪ oral pyridostigmine bromide
(Mestinon) is discontinued for surgery, the patient must receive an IV equivalent of the medication
Complications
• Myasthenic crisis: an exacerbation of MG weakness that provokes an acute episode of respiratory failure that is often caused by a respiratory infection from viral or bacterial agents
o Involves respiratory and bulbar muscles
o tachycardia, flaccid muscles, and pale, cool skin
o lasts for 2 weeks
o Management: IVIG or plasmapheresis
• Cholinergic Crisis: due to excessive anticholinesterase medication; secondary to the patient taking too much of the prescribed MG medication (Parasypathetic activity)
o S/S: muscle bradycardia, fasciculations (muscle twitch), sweating, pallor, excessive secretions, and small pupils
o Anticholinesterase medications are temporarily d/c
Tensilon (edrophonium) test used to distinguish between the Myasthenic and Cholinergic crisis
• muscle strength improvement: Myasthenic
• fasciculations and muscle weakness, including respiratory muscles: Cholinergic
Assessment and Analysis
• respiratory deterioration (Vital Capacity test)
o Vital capacity: the maximum amount of air exhaled following maximal inhalation
▪ Normal: 65 mL/kg
▪ Respiratory deteriation: > 15 mL/kg; >1L
• respiratory
deterioration may progress rapidly and mechanical ventilation will be required
o serial negative inspiratory force and positive expiratory force assessments w/ assistance of respiratory therapist
• muscular weakness
Assessments
Actions
Administer medications at prescribed times and prior to activities requiring swallowing Pyridostigmine must be administered exactly at the prescribed hour to maintain optimal muscle strength. Often patients take pyridostigmine 30 to 60 minutes before meals to minimize difficulty
with chewing and swallowing.
Elevate head of patient’s bed with eating
or drinking Weakness of the oropharyngeal muscles increases the risk of
aspiration.
Establish effective communication method
with patient Consult with Speech Language Pathology to obtain a picture
communication board.
Plan meals when medications are at peak
levels Small, frequent meals will help maintain calorie intake. Weight loss
may result from poor nutritional intake
Offer soft foods and thickened liquids as recommended by speech language
pathologist A temporary feeding tube may be necessary if swallowing is impaired or if the patient deteriorates and requires intubation and
mechanical ventilation.
Plan for rest periods between activities of
daily living Use energy conservation techniques such as sitting while activities of
daily living are completed to minimize fatigue and muscle weakness.
Teaching
Importance for taking medications as prescribed It is important to teach the patient to adhere to the medication schedule at home as swallowing may be impaired if eating, drinking, brushing teeth,
etc. are not performed at peak levels of the medications.
Educate patient to keep medication with him/her at all times. Spare doses should be kept at place of employment and in the car. When the patient travels, medication should remain with the
patient in carry-on luggage. Patient should not miss a dose of pyridostigmine bromide as this can lead to muscular weakness.
Instruct patient to purchase a
MedicAlert bracelet and to wear it daily In the event of an emergency, the patient’s diagnosis may be rapidly
identified by emergency medical service providers.
Avoid public places such as theaters or concerts in the winter where there are
large gatherings of people Patient may be subjected to colds and flu where there are large gatherings of people and this increases risk of exacerbation.
Obtain vaccines to prevent flu and
pneumonia Decreases the risk of infection. Respiratory infections may lead to
myasthenic crisis that requires hospitalization.
Prevent fatigue with frequent rest periods. Recognize physical limits and plan activities during peak energy
periods. Decreases risk of injury as activities are scheduled during peak times of medications.
Do not take any over-the-counter preparations without first checking with
provider Over-the-counter products may have ingredients that are contraindicated in MG
Inform patient and family about resources such as the Myasthenia Gravis
Foundation of America. This organization provides detailed education and e-resources for patients and families.
Guillain-Barré syndrome
• an acute inflammatory demyelinating polyneuropathy (simultaneous neuropathy of peripheral nerves)
• often occurs after an infection and leads to a rapidly progressing flaccid paralysis
• Respiratory or gastrointestinal infections are the most common sources
o Campylobacter jejuni
o Epstein-Barr virus
o Mycoplasma pneumonia
o Haemophilus influenzae
• Mortality rates range from 2% to 10% from autonomic dysfunction or complications of immobility and increase with age. Patients are more likely to die if they are over 60 years of age, have a rapidly progressing variant of GBS, develop axonal loss, and require an extended course of mechanical ventilation
• mediated by an immune response with acute lower extremity weakness with areflexia or diminished reflexes developing over several days
• Schwann cell invade the myelin, resulting in demyelination
o Sensory function also impaired
• Nerve damage results in numbness and tingling, muscle weakness, paralysis, and potential respiratory compromise
Stages
1. acute stage: starts with the onset of signs and symptoms of peripheral nerve demyelination (destruction of myelin sheath), edema, and inflammation.
a. Lasts for 4 weeks
2. plateau stage: demyelination ceases
a. lasts for a few days to weeks (2 weeks)
3. recovery stage: remyelination and axonal regeneration begins and there is gradual improvement in the patient’s signs and symptoms
Clinical Manifestations
• symmetrical ascending motor weakness and paralysis that usually starts in the feet and extends to the trunk and arms
o “starts in the toes, and up it goes”
• paresthesia’s and pain that involves the shoulders, back, buttocks, and upper legs
• diminished or absent deep tendon reflexes (areflexia): KEY FINDING
• CN VII (facial nerve) is most commonly affected
o problems with facial expressions such as smiling or frowning
• CN IX to XII involvement
o Causing dysphagia
• CN X involvement
o may exhibit autonomic dysfunction with possible cardiac dysrhythmias, paroxysmal hypotension, orthostatic hypotension, paralytic ileus, urinary retention, and SIADH
• respiratory impairment
Diagnostic Tests
• progressive weakness of two or more limbs caused by neuropathy, areflexia, and history of recent viral or bacterial infection
• CSF analaysis
o elevated protein and normal cell count
• Electromyography
o reveal slowed nerve conduction velocity soon after the patient develops paralysis
Medications
• IVIG
o can shorten the length of the recovery phase by 50%, and this therapy is recommended for patients who need help to walk within 2 to 4 weeks of symptom onset
o Mechanisms in which it works: blocking of macrophage receptors, the inhibition of antibody production, the inhibition of complement binding, and the neutralization of pathologic antibodies
o Dosing: 2 g/kg IV for 5 days
o Adverse S/S: flu like symptoms, aseptic meningitis and acute renal failure, fluid overload in pts with HF or renal insufficiency
• Plasmapheresis
o Recommended for nonambulatory adult patients who start treatment within 4 weeks of onset of neuropathic symptoms & for ambulatory patients who start treatment within 2 weeks of the onset of neuropathic symptoms
o diminishes the length of hospitalization and the need for mechanical ventilation if initiated within the first week of symptoms
o risk for infection and hemorrhage
o adverse effects: hypotension, bradycardia, fever, chills, and rash
o complications: septicemia, pneumonia, cardiac arrhythmias, malaise, bleeding/clotting abnormalities, and hypocalcemia
Complications
• risk of respiratory compromise
o airway needs to be maintained, and the patient may require intubation and mechanical ventilation to prevent respiratory arrest
Assessment and Analysis
• Respiratory muscle weakness
• Skeletal muscle weakness (often ascending)
• Pain
• Autonomic manifestations such as sweating and tachycardia
• VTE
o SQ Heparin
o Antiembolism stockings and sequential compression devices
• Pressure ulcers
• autonomic manifestations
o patient’s clothing and linens require frequent changes to prevent areas of moisture and to promote skin integrity
Assessments
Cranial nerves VII, IX, X, XI, and
XII Cranial nerve assessment should be performed to identify deficits. Focus on facial
expression, speech, gag, and swallow.
Perform respiratory assessment with vital capacity measurement Respiratory assessment is a priority because respiratory compromise may require intubation. Vital capacity measurement is an important function to monitor. The provider should be notified of a value below 1 L. Diaphragmatic weakness results in
hypoxemia.
Motor and sensory assessment Perform motor and sensory assessments to identify weakness and sensory
involvement
Pain assessment Patients often complain of pain. This may be due to sensory nerve fiber
involvement.
Actions
Reposition patient frequently Measures are implemented to promote comfort and to prevent complications of immobility including thromboembolism and impaired skin
integrity.
Discuss use of analgesics or
nonopioids with provider Carbamazepine or gabapentin may be used to relieve neuropathic pain.
Offer diversions such as music or
other relaxation techniques Pain management is addressed with pharmacological as well as
nonpharmacological methods.
Turn frequently and perform range of motion every shift to maintain
joint and muscle integrity Immobility places the patient at risk for contractures, skin breakdown, and VTE.
Discuss with provider need for VTE prevention (subcutaneous heparin, antiembolism hose, sequential
compression devices) Prolonged immobility leads to venous stasis and development of VTE
Establish method of communication and provide method to call nurse,
e.g., soft call bell Because of limb weakness, patient may not have the strength to locate and use the call light. A soft squeeze call bell allows the patient to call the nurse
with only a gentle squeeze.
Teaching
Educate the patient and family about GBS at each stage of the
illness Education allows the patient and family to anticipate that respiratory deterioration may occur. Having this information
ahead of time may help to alleviate fear.
Inform the patient and family about the importance of respiratory monitoring in the acute phase Provide encouragement that the disease course lasts several weeks to months and rehabilitation will assist the patient in returning to premorbid functioning. In addition, it is important to inform the patient and family that recovery is possible from this
neurological disorder.
Inform patient and family about resources such as the GBS
Foundation International Community and other resources provide additional support systems for the patient and family. Respite care may be available
through some of these organizations
Trigeminal Neuralgia
• CN 5 (trigeminal nerve) emerges from the pons of the brainstem and has three branches
o the ophthalmic, maxillary, and mandibular branches
• mixed cranial nerve: has both motor and
sensory innervation that is responsible for facial sensation and strength of the jaw
• more common in women than in men;
rarely affects in ages >50 years
o risk factors: hypertension and MS
• a sudden, usually unilateral, severe, brief, stabbing, recurrent pain in the distribution of one or more branches of the trigeminal nerve (CN V); atypical pain, which is a constant burning sensation that covers a more diffuse region of the face
• etiology: unknown; can be due to vascular
compression
o associated with a tumor, structural abnormality of the skull base, or MS
Clinical Manifestations
• Spontaneous pain or onset of symptoms followed dental surgery, facial trauma, or a motor vehicle accident
• sharp, throbbing, and shocklike pain
o triggers: touching an area of the skin or an activity such as brushing the teeth, drinking a beverage, smiling, or talking
• breeze from opening the door triggers the pain
• One attack per day or as many as 10 to 15 attacks an hour
Hygiene activities such as brushing the teeth, bathing, and shaving may be neglected because they trigger pain
Medical Management
• antiepileptic drugs: carbamazepine, oxcarbazepine, or gabapentin
o Carbamazepine: FIRST LINE; works by reducing the excitability of neurons by inhibiting neuronal sodium channels
▪ baclofen may be also be
prescribed, particularly in patients with MS as it works as a muscle relaxant
Procedures to Treat Trigeminal Neuralgia
• surgery
o Microvascular decompression: most effective
▪ facial pain is usually relieved
within 24 to 48 hours, and the patient does not have residual facial numbness
Assessment and Analysis
• Examination of the cranial nerves identifies the area of the face that is affected
• short-stabbing attacks of pain; unilateral and may correlate to a specific CN V branch sensory distribution
Assessments
Pain, including onset, character,
and exacerbating factors It is important to identify the pain rating as well as aggravating factors. The pain is
believed to be related to irritation of the nerve fibers in CN V.
History of exacerbations and
remissions Because the time between attacks appears to shorten as the patient ages, it is
important to establish any pattern of attacks.
Oral intake Pain may impair oral intake so it is important to assess oral intake and fluid volume
status
Weight If pain significantly interferes with nutritional intake, the patient may have weight
loss
Actions
Administer medications as ordered Medication is taken at prescribed intervals to assist with pain relief. Antiepileptic medications have been found to
have an analgesic effect on neuropathic pain.
Nonpharmacological strategies including meditation, diversional activities, support groups and acupuncture. Suggest meditation or diversional activities
Seek a support group so that members may share their experiences
Acupuncture has been found to have efficacy similar to
that of Tegretol. These interventions are implemented to address pain management through alternative measures. Acupuncture has been found to have efficacy similar to that of carbamazepine in some patients.
Teaching
Identify and avoid exacerbating factors (cold weather, drafts,
etc). Because the pain can be severe and interfere with activities of daily living, it is important to minimize factors that cause or exacerbate
the pain associated with this disorder
The pain from trigeminal neuralgia can affect the patient’s quality of life The nurse educates the patient about the medications that are prescribed, including side effects. Although AEDs are used for pain management, the patient should be educated that the indication is neuropathic pain, not epilepsy. The nurse may also suggest
alternative methods of hygiene that may not aggravate an attack
[Show More]



.png)

.png)

.png)


 Med Surg test Latest Verified Questions and all Correct Answers with Explanations Chapter 38 Assessment and Management of Patients with Rh.png)




, Latest Questions and Answers with Explanations.png)


.png)