SOAP Note Template
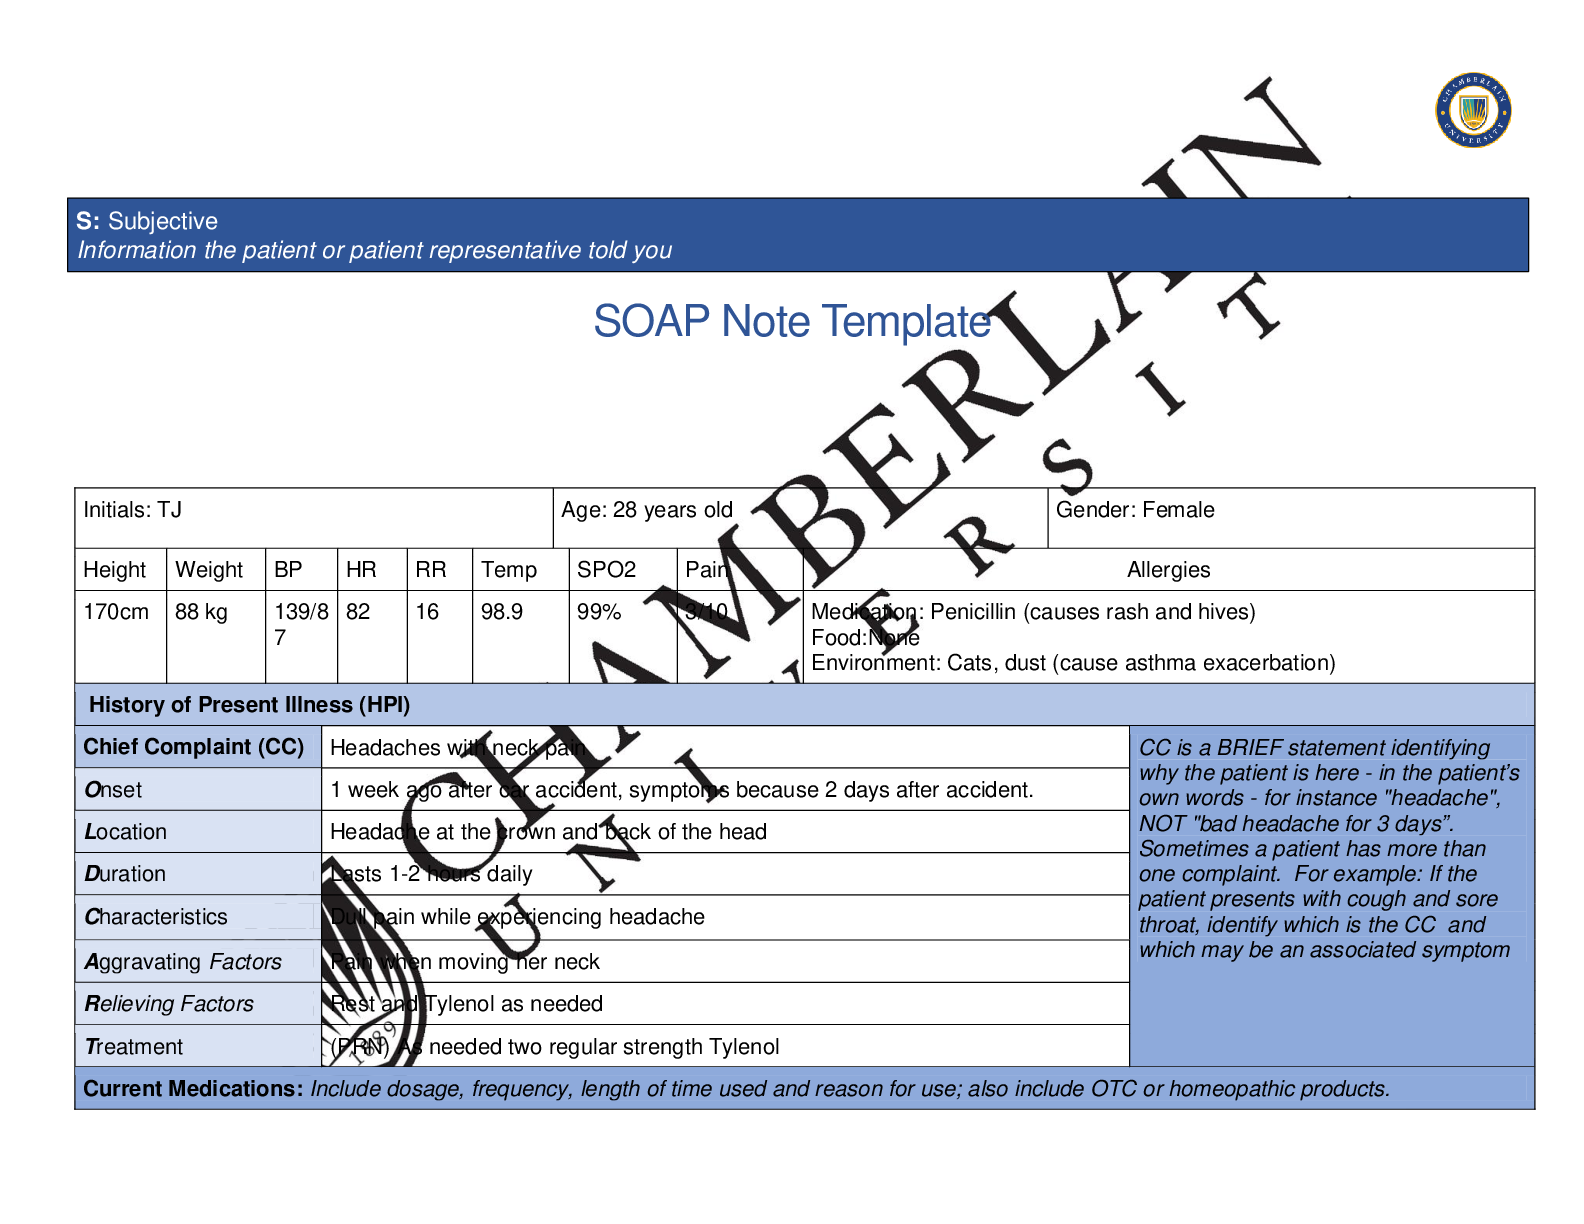
Initials: TJ Age: 28 years old Gender: Female
Height Weight BP HR RR Temp SPO2 Pain Allergies
170cm 88 kg 139/8
7
82 16 98.9 99% 3/10 Medication: Penicillin (causes rash and hives)
Food:None
Env
...
SOAP Note Template
Initials: TJ Age: 28 years old Gender: Female
Height Weight BP HR RR Temp SPO2 Pain Allergies
170cm 88 kg 139/8
7
82 16 98.9 99% 3/10 Medication: Penicillin (causes rash and hives)
Food:None
Environment: Cats, dust (cause asthma exacerbation)
History of Present Illness (HPI)
Chief Complaint (CC) Headaches with neck pain CC is a BRIEF statement identifying
why the patient is here - in the patient’s
own words - for instance "headache",
NOT "bad headache for 3 days”.
Sometimes a patient has more than
one complaint. For example: If the
patient presents with cough and sore
throat, identify which is the CC and
which may be an associated symptom
Onset 1 week ago after car accident, symptoms because 2 days after accident.
Location Headache at the crown and back of the head
Duration Lasts 1-2 hours daily
Characteristics Dull pain while experiencing headache
Aggravating Factors Pain when moving her neck
Relieving Factors Rest and Tylenol as needed
Treatment (PRN) As needed two regular strength Tylenol
Current Medications: Include dosage, frequency, length of time used and reason for use; also include OTC or homeopathic products.
S: Subjective
Information the patient or patient representative told youMedication
(Rx, OTC, or Homeopathic) Dosage Frequency Length Used of Time Reason for Use
Proventil Inhaler 90 mcg 2 puffs as needed Every 4 hours as
needed
Wheezing
Shortness of breath
Tylenol 650 mg (states she
takes two tablets)
Once a day The past few
days
Headaches
Advil 200 mg TID PRN First couple of
days of
menstrual cycle
Cramping
Flovent inhaler
enter text.
enter
text.
here
.
Asthma
.
enter text.
enter
text.
here
.
.
Past Medical History (PMHx) – Includes but not limited to immunization status (note date of last tetanus for all adults), past major illnesses,
hospitalizations, and surgeries. Depending on the CC, more info may be needed.
Tina was diagnosed with Diabetes Mellitus type 2 at the age of 24 years old. She is non-compliant with taking her metformin, as well as checking
blood sugar on a regular basis.
Diagnosed with asthma at the age of 2 and a half. Has been taking her inhaler as needed for asthma exacerbation; currently it is not being as
effective as it was. Is now on Flovent which has been providing relief for maintenance.
Suffers from heavy periods that include cramping as well as tenderness. Tina has irregular periods which last between 9-10 days.
Immunizations are current, has received vaccinations for childhood.
Flu shot received last 5 to 6 years ago.
Last tetanus shot was about two years ago.
Last pap smear was done about 4 years ago, and was normal. Tina has Polycystic ovarian syndrome.
Social History (Soc Hx) - Includes but not limited to occupation and major hobbies, family status, tobacco and alcohol use, and any other pertinent
data. Include health promotion such as use seat belts all the time or working smoke detectors in the house.Patient denies smoking, denies recreational drug use. Patient is a former pot smoker who quit when she was 20 or 21 years old. She is occasionally
exposed to second hand smoke socially as her friends smoke. Drinks alcohol occasionally, about 6 drinks a month. Patient is currently a student
working on obtaining her bachelors degree in accounting. Patient lives with her mother and sister who support her dreams. Patient became sexually
active at the age of 18 and has had 3 male sexual partners in total. Denies using birth control at the moment.
Family History (Fam Hx) - Includes but not limited to illnesses with possible genetic predisposition, contagious or chronic illnesses. Reason for
death of any deceased first degree relatives should be included. Include parents, grandparents, siblings, and children. Include grandchildren if
pertinent.
Mother history of HTN and high cholesterol.
Father history of HTN, diabetes mellitus type 2, high cholesterol ( Passed away in car accident).
Paternal grandmother history of HTN and high cholesterol.
Paternal grandfather history of HTN, diabetes, colon cancer (passed away from colon cancer).
Brother is obese.
Sister has asthma.
Maternal grandmother history of hypertension, and high cholesterol (deceased from stroke at 73 years old)
Maternal grandfather HTN, high cholesterol.
Review of Systems (ROS): Address all body systems that may help rule in or out a differential diagnosis Check the box next to each positive
symptom and provide additional details.
Constitutional Skin HEENT☐Fatigue here
.
☐Weakness
.
☐Fever/Chills
.
☐Weight Gain
.
☐Weight Loss
.
☐Trouble Sleeping Click or
tap .
☐Night Sweats
.
☐Other:
enter
text.
☐Itching
.
☐Rashes
.
☐Nail Changes Click or
tap .
☐Skin Color Changes
enter text.
☐Other:
enter text.
☐Diplopia
.
☐Eye Pain
.
☐Eye redness
.
☐XVision changes Click
or tap .
☐Photophobia Click or
tap .
☐Eye discharge Click or
tap .
☐Earache here
.
☐Tinnitus here
.
☐Epistaxis
.
☐Vertigo here
.
☐Hearing Changes Click
or tap .
☐Hoarseness here
.
☐Oral Ulcers here
.
☐Sore Throat here
.
☐Congestion here
.
☐Rhinorrhea here
.
☐Other:
.
Respiratory Neuro Cardiovascular☐Cough enter
text.
☐Hemoptysis
enter text.
☐Dyspnea enter
text.
☐Wheezing enter
text.
☐Pain on Inspiration here
.
☐Sputum Production
Choose an item.
Choose an item.
Choose an item.
☐Other: .
☐Syncope or
Lightheadedness
.
☐XHeadache Started recently
2 days after low speed car
accident, headache occurs
daily for 1-2 hours at a time.
Pain is described as dull, and
located at the crown and back
of the head.
☐Numbness here
.
☐Tingling
enter text.
☐Sensation Changes
Choose an item.
☐Speech Deficits
.
☐Other:
enter text.
☐Chest pain enter
text.
☐SOB .
☐Exercise Intolerance here
.
☐Orthopnea enter
text.
☐Edema .
☐Murmurs enter
text.
☐Palpitations here
.
☐Faintness here
.
☐OC Changes
.
☐Claudications
.
☐PND
enter text.
☐Other:
enter text.
MSK GI GU PSYCH☐XPain Neck pain with movement
of head and neck
☐XStiffness stiffness to neck
☐Crepitus enter
text.
☐Swelling enter
text.
☐xLimited ROM
☐Redness
enter text.
☐Misalignment
enter text.
☐Other: enter
text.
☐Nausea/Vomiting
enter text.
☐Dysphasia enter
text.
☐Diarrhea enter
text.
☐Appetite Change
enter text.
☐Heartburn enter
text.
☐Blood in Stool
enter text.
☐Abdominal Pain
enter text.
☐Excessive Flatus
enter text.
☐Food Intolerance
enter text.
☐Rectal Bleeding
enter text.
☐Other:
.
☐Urgency
enter text.
☐Dysuria
enter text.
☐Burning
enter text.
☐Hematuria here
.
☐Polyuria
enter text.
☐Nocturia
enter text.
☐Incontinence
.
☐Other:
enter text.
☐Stress
enter text.
☐Anxiety
enter text.
☐Depression here
.
☐Suicidal/Homicidal Ideation
.
☐Memory Deficits
.
☐Mood Changes
.
☐Trouble Concentrating Click
or tap .
☐Other:
enter text.
GYN
☐Rash .
☐Discharge .
☐Itching .
☐Irregular Menses .
☐Dysmenorrhea .
☐Foul Odor .
☐Amenorrhea .
☐XLMP: N/A
☐Contraception .
☐Other:.Body System Positive Findings Negative Findings
General
. .
Skin
. .
HEENT
. .
Respiratory
. .
O: Objective
Information gathered during the physical examination by inspection, palpation, auscultation, and palpation. If a body
system, write “”. Document pertinent positive and negative assessment findings.Neuro Cranial nerve 2 (optic) Right Fundus has cotton wool bodies
present.
Decreased sensation to bilateral feet.
Tina is oriented to person, place and time
Her abstract thinking responses were intact and relevant
She is able to follow simple commands
Attention span was accurate, intact as well as general
knowledge was accurate
Remote memory and immediate memory are intact
Vocabulary is complex as expected for her age, education
level and general ability.
No apparent problems with pronunciation or expression.
Cranials Nerves:
Olfatory I: sense of smell is intact, nose symmetrical
bilaterally
Optic II: Right eye 20/40 , left eye 20/20, no visible
abnormal findings on the left fundus, and sharp disc
margins noted bilaterally.
Optic II and Oculomotor III: PERRLA pupils reactive to light
bilaterally.
III (Oculomotor), IV (Trochlear) and VI (Abducens) Cardinal
fields and convergence equal bilaterally
Trigeminal V: Facial sensation intact
Facial VII: Skull and facial feature symmetric
Auditory VIII: Weber test and bilateral Rinne test normal
Glossopharyngeal IX and Vagus X Gag reflex intact
Spinal AccessoryXI: Shoulder shrugging symmetric, 5-full
range of motion against gravity, with resistance and Neck
strength, 5-full range of motion against gravity, with
resistance
Hypoglossal XII:Tongue symmetric with no abnormalities
Expected deep tendon reflexes to bilateral triceps, bilateral
biceps, bilateral brachioradialis, bilateral patellar, and
bilateral Achilles tendon
Point-to-point movements smooth and accurate bilaterally
Tina was able to perform coordination with rapid alternating
hand movements without difficulty
Her gait observed to be steady with continuous, symmetric
stepsGraphesthesia indentified bilaterally
Expected sensation in proximal and distal bilateral arms and
legs to dull, soft, and sharp touch.
Position sense intact in fingers and toes
Stereognosis intact bilaterallyCardiovascular
. .
Musculoskeletal
. .
Gastrointestinal
. .
Genitourinary
Psychiatric
Gynecological
Problem List
1. Headache 6 Hypertension 11 Activity intolerance
2 Diabetes Mellitus type 2 7 Stress 12 .
3 Asthma 8 Dysmenorrhea 13 .
4 Neck pain 9 Menorrhagia 14 .
5 Obesity 10 Polycystic Ovarian Syndrome 15 .Diagnosis ICD-10 Code Pertinent Findings
Traumatic Headache (Acute
post)
G44.31 Chief complain of headaches, pain is on the crown of the head
and back of the head. It started a couples of days after the low
speed accident lasting from 1 to 2 hours daily.
Strain of muscle, fascia and
tendon at the neck level
S16.1 Chief complain is pain that is located on the back of the neck
muscles when moving the head and neck
P: Plan
Address all 5 parts of the comprehensive treatment plan. If you do not wish to order an intervention for any part of the treatment plan, write “None
at this time” but do not leave any heading blank. No intervention is self-evident. Provide a rationale and evidence-based in-text citation for each
intervention.
A: Assessment
Medical Diagnoses. Provide 3 differential diagnoses which may provide an etiology for the CC. The first diagnosis (presumptive
diagnosis) is the diagnosis with the highest priority. Provide the ICD-10 code and pertinent findings to support each diagnosis.Type 2 Diabetis Mellitus with
unspecified diabetic retinopathy
E 11.31 Cotton wool spots noted on the right fundus upon examination
with opthalmoscope
Diagnostics: List tests you will order this visit
Test Rationale/Citation
Medications: List medications/treatments including OTC drugs you will order and “continue previous meds” if pertinent.
Drug Dosage Length of Treatment Rationale/CitationIbuprofen 400 mg Take one tablet every 4-6 hours
for pain or headaches
Ibuprofen is effective in decreasing
the number of headaches daily as
well as the intensity.
Manzano, S., Doyon-Trottier, E., &
Bailey, B. (2010). Myth: Ibuprofen
is superior to acetaminophen for
the treatment of benign headaches
in children and adults. CJEM:
Canadian Journal of Emergency
Medicine, 12(3), 220–222.
https://doiorg.chamberlainuniversity.idm.oclc.
org/10.1017/S1481803500012276
Robaxin 500mg QID ( 4 times a day) As per the article the use of muscle
relaxants are stated to be effective
with managing acute pain.
Kumbham, S., Ghate, V., & Lewis,
S. A. (2019). Approaches for the
Delivery of Skeletal Muscle
Relaxants: A Review. Indian
Drugs, 56(7), 7–15. Retrieved from
https://search-ebscohostcom.chamberlainuniversity.idm.ocl
c.org/login.aspx?direct=true&db=a
9h&AN=137805231&site=ehostlive&scope=site
. . . .Referral/Consults:
Consult with a Neurologist for headaches that continue to persist after 4
weeks
Ophthalmologist
Rationale/Citation Tina should follow up with a
neurologist if the headaches and
pain persist for another 4 weeks.
Tina needs further workup with an
ophthalmologist in order to receive
a comprehensive dilated eye
exam. By having her pupils dilated
the ophthalmologist will have a
clearer view of her eyes, and then
be able to get a better picture of
the eyes.
Ho, K. C., Stapleton, F., Wiles, L.,
Hibbert, P., Alkhawajah, S., White,
A., & Jalbert, I. (2019). Systematic
review of the appropriateness of
eye care delivery in eye care
practice. BMC Health Services
Research, 19(1), N.PAG.
https://doiorg.chamberlainuniversity.idm.oclc.
org/10.1186/s12913-019-4493-3
Education:Patient has been educated to be careful when taking robaxin as it can
cause drowsiness and dizziness. Robaxin could also impair the patients
mental status; This medication should be taken with precaution, avoid
driving when on this medication.
Patient instructed to return to the clinic if the signs and symptoms
persist, if not to go to the ER.
Patient was instructed to report any new changes in her level of
consciousness, example such as if she is not capable to keep her
balance, if she develops double vision, or sudden confusion to urgently
go the nearest emergency department.
Rationale/Citation Patient needs to have a clear
understanding of possible side
effects, and so follow the education
provided in order to increase
quality of life. Patient should also
be aware of when to visit the ER in
case of emergency.
Follow Up: Indicate when patient should return to clinic and provide detailed instructions indicating if the patient should return sooner than
scheduled or seek attention elsewhere.
Tina should return to the clinic and follow up in 2 weeks.
Follow up with neurologist as well as ophthalmologist.
Return to the clinic in case of emergency if any adverse effects arise.
Rationale/Citation The provider should see Tina in 2
weeks as follow up to check is
medications are working properly.
Also, to assess the severity of the
headaches and neck pain. See if
there is some relief, if not it is
important to follow up with
neurology for a more in depth
treatment.
References
Include at least one evidence-based peer-reviewed journal article which relates to this case. Use the correct APA 6th edition formatting.Manzano, S., Doyon-Trottier, E., & Bailey, B. (2010). Myth: Ibuprofen is superior to acetaminophen for the treatment of benign headaches in
children and adults. CJEM: Canadian Journal of Emergency Medicine, 12(3), 220–222. https://doiorg.chamberlainuniversity.idm.oclc.org/10.1017/S1481803500012276
Kumbham, S., Ghate, V., & Lewis, S. A. (2019). Approaches for the Delivery of Skeletal Muscle Relaxants: A Review. Indian Drugs, 56(7), 7–15.
Retrieved from https://search-ebscohost-com.chamberlainuniversity.idm.oclc.org/login.aspx?direct=true&db=a9h&AN=137805231&site=ehostlive&scope=site
Ho, K. C., Stapleton, F., Wiles, L., Hibbert, P., Alkhawajah, S., White, A., & Jalbert, I. (2019). Systematic review of the appropriateness of eye care
delivery in eye care practice. BMC Health Services Research, 19(1), N.PAG. https://doi-org.chamberlainuniversity.idm.oclc.org/10.1186/s12913-
019-4493-3
.
[Show More]