SOAP Note Template
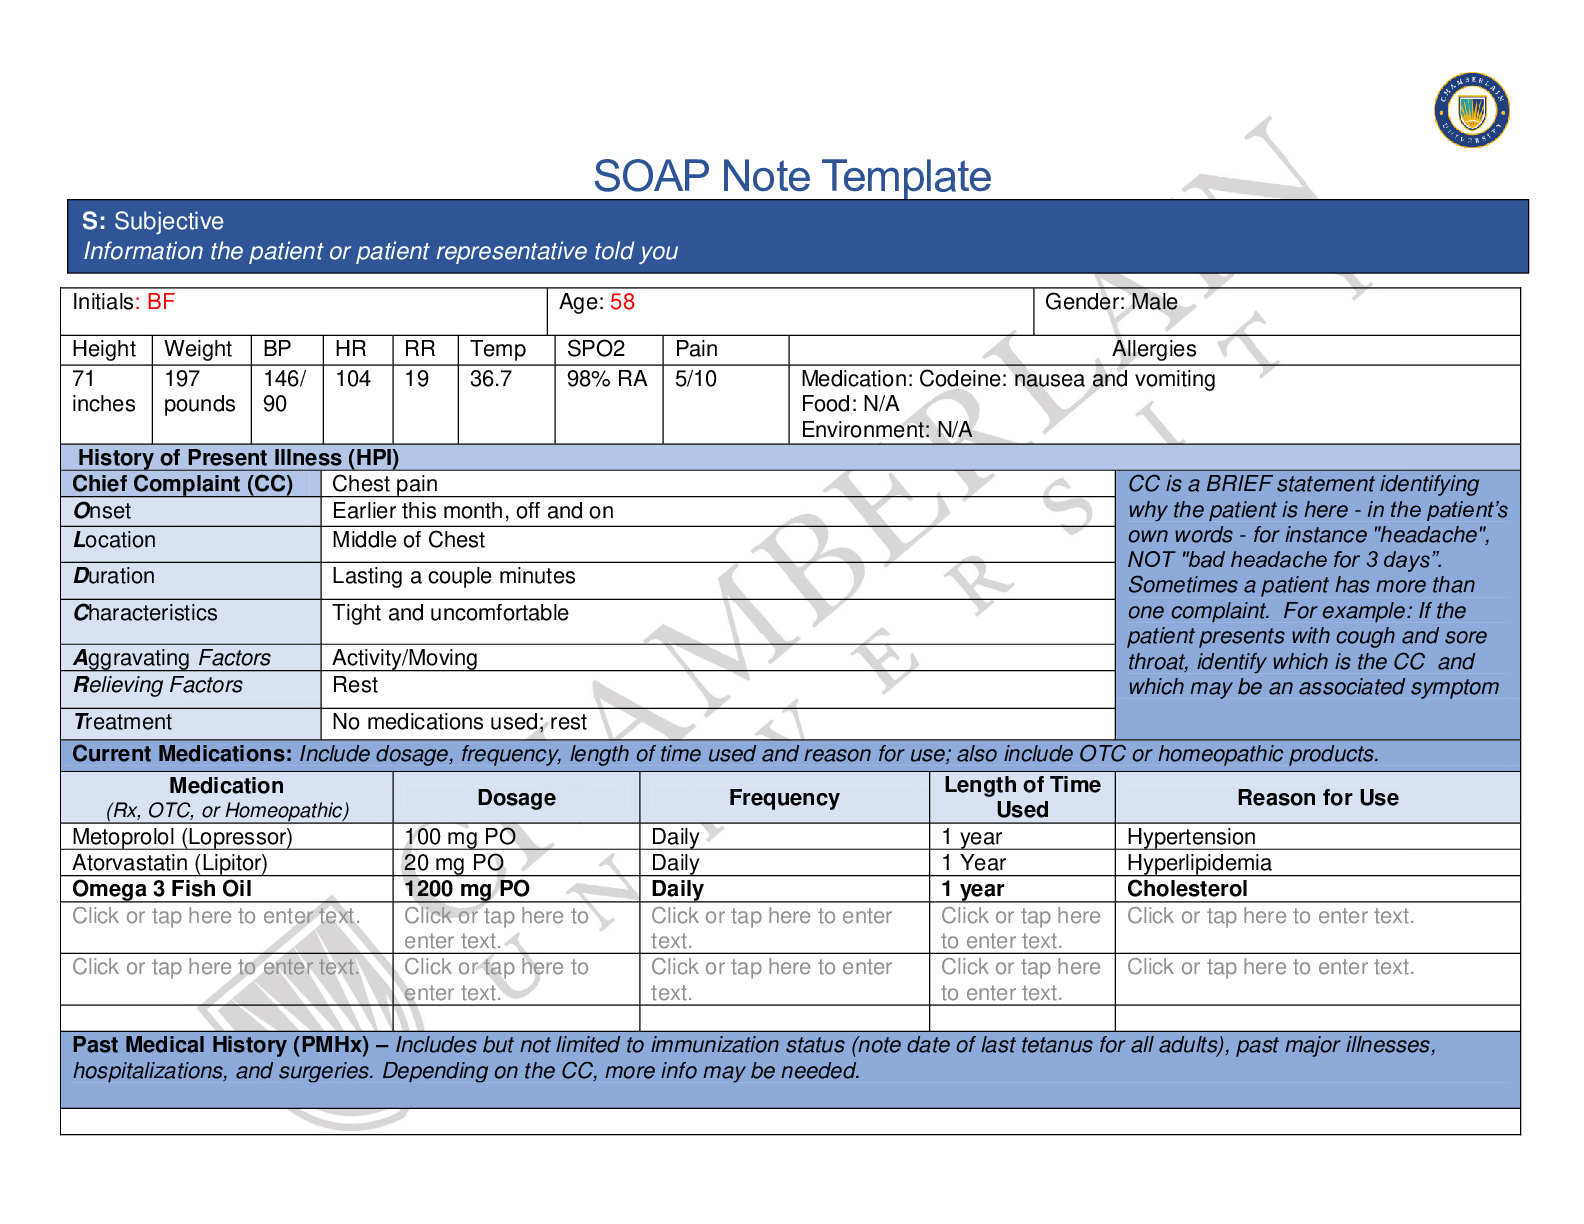
Initials: BF Age: 58 Gender: Male
Height Weight BP HR RR Temp SPO2 Pain Allergies
71
inches
197
pounds
146/
90
104 19 36.7 98% RA 5/10 Medication: Codeine: nausea and vomiting
Food: N/A
Envi
...
SOAP Note Template
Initials: BF Age: 58 Gender: Male
Height Weight BP HR RR Temp SPO2 Pain Allergies
71
inches
197
pounds
146/
90
104 19 36.7 98% RA 5/10 Medication: Codeine: nausea and vomiting
Food: N/A
Environment: N/A
History of Present Illness (HPI)
Chief Complaint (CC) Chest pain CC is a BRIEF statement identifying
why the patient is - in the patient’s
own words - for instance "headache",
NOT "bad headache for 3 days”.
Sometimes a patient has more than
one complaint. For example: If the
patient presents with cough and sore
throat, identify which is the CC and
which may be an associated symptom
Onset Earlier this month, off and on
Location Middle of Chest
Duration Lasting a couple minutes
Characteristics Tight and uncomfortable
Aggravating Factors Activity/Moving
Relieving Factors Rest
Treatment No medications used; rest
Current Medications: Include dosage, frequency, length of time used and reason for use; also include OTC or homeopathic products.
Medication
(Rx, OTC, or Homeopathic) Dosage Frequency Length of UsedTime Reason for Use
Metoprolol (Lopressor) 100 mg PO Daily 1 year Hypertension
Atorvastatin (Lipitor) 20 mg PO Daily 1 Year Hyperlipidemia
Omega 3 Fish Oil 1200 mg PO Daily 1 year Cholesterol
.
.
.
to .
.
to .
.
Past Medical History (PMHx) – Includes but not limited to immunization status (note date of last tetanus for all adults), past major illnesses,
hospitalizations, and surgeries. Depending on the CC, more info may be needed.
S: Subjective
Information the patient or patient representative told youPatient stated current and up to date with immunizations including annual flu shot and tetanus (10/2014). All childhood immunizations were
received. Patient denies past surgical history or hospitalizations. No past history of angina.
Social History (Soc Hx) - Includes but not limited to occupation and major hobbies, family status, tobacco and alcohol use, and any other pertinent
data. Include health promotion such as use seat belts all the time or working smoke detectors in the house.
Patient denies smoking and smokeless tobacco use; denies illicit drug use including marijuana. Patient stated drinking approximately 2-3 beers per
week.
Family History (Fam Hx) - Includes but not limited to illnesses with possible genetic predisposition, contagious or chronic illnesses. Reason for
death of any deceased first degree relatives should be included. Include parents, grandparents, siblings, and children. Include grandchildren if
pertinent.
Father: deceased at 75 (colon cancer); PMH: hypertension, hyperlipidemia, obesity
Mother: alive (80 y/o); PMH: DM type 2, hypertension
Brother: deceased at 24- MVC
Sister: alive (52 y/o); PMH: DM type 2, hypertension
Maternal grandmother: deceased age 65- breast cancer
Maternal grandfather: deceased age 54- MI
Paternal grandmother: deceased age 78- pneumonia
Paternal grandfather: deceased age 85- natural causes
Son: alive, age 26; no PMH
Daughter: alive, age 19; PMH: asthma
Review of Systems (ROS): Address all body systems that may help rule in or out a differential diagnosis Check the box next to each positive
symptom and provide additional details.
Constitutional Skin HEENT
☐Fatigue
to .
☐Weakness
.
☐Fever/Chills
.
☒Weight Gain approx. 20
pounds over last year or so
☐Weight Loss
.
☐Itching
.
☐Rashes
.
☐Nail Changes Click
or tap
.
☐Skin Color Changes
.
☐Diplopia
.
☐Eye Pain
.
☐Eye redness Click or
tap .
☐Vision changes Click or
tap .
☐Photophobia Click or
tap .
☐Earache
to .
☐Tinnitus
to .
☐Epistaxis
.
☐Vertigo
to .
☐Hearing Changes Click
or tap .
☐Hoarseness
to .
☐Oral Ulcers
to .
☐Sore Throat
to .
☐Congestion
to .
☐Rhinorrhea
to .☐Trouble Sleeping Click or
tap .
☐Night Sweats
.
☐Other:
.
☐Other:
.
☐Eye discharge Click or
tap .
☐Other:
.
Respiratory Neuro Cardiovascular
☐Cough
.
☐Hemoptysis
.
☐Dyspnea
.
☐Wheezing
.
☐Pain on Inspiration
to .
☐Sputum Production
.
.
.
☐Other:
.
☐Syncope or
Lightheadedness
.
☐Headache
to .
☐Numbness
to .
☐Tingling
.
☐Sensation Changes
.
☐Speech Deficits
.
☐Other:
.
☒Chest pain intermittent x 1 month,
approx. 3 episodes
☐SOB .
☐Exercise Intolerance
to .
☐Orthopnea
.
☐Edema .
☐Murmurs
.
☐Palpitations
.
☐Faintness
to .
☐OC Changes
.
☐Claudications
.
☐PND
.
☐Other:
.
MSK GI GU PSYCH
☐Pain
.
☐Stiffness
.
☐Crepitus
.
☐Swelling
.
☐Nausea/Vomiting
.
☐Dysphasia
.
☐Diarrhea
.
☐Appetite Change
.
☐Urgency
.
☐Dysuria
.
☐Burning
.
☐Hematuria
to .
☐Stress
.
☐Anxiety
.
☐Depression
to .
☐Suicidal/Homicidal Ideation
.☐Limited ROM .
☐Redness
.
☐Misalignment
.
☐Other:
.
☐Heartburn
.
☐Blood in Stool
.
☐Abdominal Pain
.
☐Excessive Flatus
.
☐Food Intolerance
.
☐Rectal Bleeding
.
☐Other:
.
☐Polyuria
.
☐Nocturia
.
☐Incontinence
.
☐Other:
.
☐Memory Deficits
.
☐Mood Changes
.
☐Trouble Concentrating Click
or tap .
☐Other:
.
GYN
☐Rash .
☐Discharge .
☐Itching .
☐Irregular Menses .
☐Dysmenorrhea .
☐Foul Odor .
☐Amenorrhea .
☐LMP: .
☐Contraception .
☐Other:.
Body System Positive Findings Negative Findings
General
. Approximately 20 pound weight gain over last couple of years Patient denies Fever, chills, fatigue
Skin
. N/A Inspection of upper body revealed no abnormalities
HEENT
.
O: Objective
Information gatd during the physical examination by inspection, palpation, auscultation, and palpation. If unable to assess a body
system, write “Unable to assess”. Document pertinent positive and negative assessment findings.Respiratory
. Auscultation: fine crackles noted at bilateral posterior bases Auscultation: clear lung sounds throughout anteriorly; clear lung
sounds upper posterior
Neuro.
Cardiovascular
Ausculatation points (aortic, pulmonic, Erb’s point, Tricuspid, mitral):
revealed S3 heart sounds, ventricular gallop
Carotid Auscultation: Right sided positive for bruit
Abdominal Aorta auscultation: positive for bruit
Palpation: Right carotid artery positive for thrill (3+)
Popliteal, Tibial, and Dorsalis Pedis artery palpation: no thrill,
amplitude 1+ bilaterally
Auscultation: left carotid- no bruit noted; no bruit noted in right
renal artery, left renal arter, right iliac artery, left iliac artery, right
femoral artery, left femoral artery
Inspection: No JVD noted (3cm at sternal angle), chest
symmetrical with no abnormalities
Capillary refill less than 3 seconds (both hands and feet)
No edema noted on bilateral lower extremities
Palpation: Left carotid artery negative for thrill (2+); PMI:
displaced laterally, 3 cm; brisk and tapping
Brachial, Radial, and Femoral artery palpation: no thrill,
amplitude 2+ bilaterally
EKG: regular sinus rhythm with no ST elevation
Skin tugor WNL
Musculoskeletal
.
Gastrointestinal
.
N/A Inspection: abdomen is symmetrical in shape, rounded
Abdominal palpation: no areas of tenderness or palpable
masses; kidneys and spleen not palpable, liver palpable
Auscultation: no friction rub noted with liver or spleen
Percussion: All areas generally tympanic
Genitourinary
.
Psychiatric
.
N/A Denies SI/HI, depressionProblem List
1. Intermittent Chest Pain 6 . 11 .
2 Fine Crackles in B/L bases 7 . 12 .
3 abnormal heart sounds (S3) 8 . 13 .
4 carotid bruit (right) 9 . 14 .
5 . 10 . 15 .
Diagnostics: List tests you will order this visit
Test Rationale/Citation
Troponin To see if the patient has any cardiac ischemia; rule out NSTEMI
BNP Adventitious lung sounds with abnormal heart sounds- rule out CHF
Chest X-ray Adventitious lung sounds, rule ou inflammatory process
Crotid ultrasound Possible carotid artery stenosis or occlusion; positive right side bruit. Gunduz et al., (2019) noted t
Gynecological
.
, N/A , N/A
Diagnosis ICD-10 Code Pertinent Findings
Angina Pectoris, unspecified I20.9 Intermittent chest pain; increased with activity, relieved with rest
Abnormal heart sounds R01.2 S3, ventricular gallop noted on auscultation
Carotid Artery Syndrome,
hemispheric
G45.1 Right carotid artery bruit noted on auscultation
P: Plan
Address all 5 parts of the comprehensive treatment plan. If you do not wish to order an intervention for any part of the treatment plan, write
“None at this time” but do not leave any heading blank. No intervention is self-evident. Provide a rationale and evidence-based in- citation for
each intervention.
A: Assessment
Medical Diagnoses. Provide 3 differential diagnoses which may provide an etiology for the CC. The first diagnosis (presumptive
diagnosis) is the diagnosis with the highest priority. Provide the ICD-10 code and pertinent findings to support each diagnosis.is a high risk correlation between patients with carotid artery stenosis and coronary artery disease.
This study showed that doppler/ultrasound can be utilized in assisting proper course of treatment
(stenting versus medical management).
Echocardiogram Abnormal heart sounds on auscultation- possible valvular disease
Medications: List medications/treatments including OTC drugs you will order and “continue previous meds” if pertinent.
Drug Dosage Length of Treatment Rationale/Citation
Nitroglycerin 0.4 mg sublingual: 1 tab every 5
minutes x 3 PRN
PRN Acute attacks of chest pain can be
relieved by sublingual nitroglycerin
and help promote vasodilation of
possible spasm (Malik, Porter,
Pavlides, & Chatzizisis, 2017).
Continue previous medications . . .
Referral/Consults:
Cardiology Rationale/Citation Pertinent for follow up of
intermittent chest pain/stable
angina. Possible need for further
evaluation and treatment with
invasive diagnostics and
intervention.
Education:
Diet for cardiac patients Rationale/Citation Patient may need additional
information related to cholesterol
and heart healthy diet. History of
high cholesterol puts patient at
risk for plaque buildup in arteries.
Follow Up: Indicate when patient should return to clinic and provide detailed instructions indicating if the patient should return sooner than
scheduled or seek attention elsew.
1 week Rationale/Citation Follow up on blood work. If chest
pain occurs, take SL nitro and go
to nearest Emergency
Department.
References
Include at least one evidence-based peer-reviewed journal article which relates to this case. Use the correct APA 6th edition formatting.
Gunduz, Y., Akdemir, R., Gunduz, H., Varim, P., Ayhan, L., Cakar, M., … Kilic, H. (2019). Relationship between carotid artery doppler flow
velocity and extent of coronary artery disease. Pakistan Heart Journal, 52(2), 124–131. Retrieved from https://search-ebscohostcom.chamberlainuniversity.idm.oclc.org/login.aspx?direct=true&db=a9h&AN=138683220&site=eds-live&scope=site
Malik, S., Porter, T., Pavlides, G., & Chatzizisis, Y. (2017). Vasospastic angina presenting with syncope and chest pain: A case report and brief
literature review. South Dakota Medicine: The Journal Of The South Dakota State Medical Association, 70(11), 498–502. Retrieved from
https://search-ebscohost-com.chamberlainuniversity.idm.oclc.org/login.aspx?direct=true&db=mdc&AN=29088521&site=eds-live&scope=site
[Show More]